
Riboflavin , reported single-ingredient oral supplementation,
does it really help with 16-week research-visit peripheral cuff systolic blood pressure in hypertensive MTHFR 677TT adults?
research showsOne trial in hypertensive MTHFR 677TT adults, predominantly taking antihypertensives but including a small untreated fraction, reported lower systolic pressure with 1.6 mg/day for 16 weeks versus placebo. The direction-normalized between-group result is −5.6 mmHg (P=0.033). This is investigator-measured research-visit cuff pressure (office-type; exact physical site unverified), not ambulatory or self-measured home-series pressure. With the evidence limitations, the current grade is C and fixed score 46. [S01–S02]
ads claimNo commercial advertising sample was researched, so no claim is made about what actual advertisements say. This page does not establish treatment of all hypertension, stroke prevention or replacement of antihypertensive medication.
Four separate assessment dimensions
| Effect direction and size | Original Table3 mean(SEM) values are141.8(2.9)→137.1(3.0) with riboflavin and143.5(3.0)→144.3(3.1) mmHg with placebo. The reported overall reduction is5.6±2.6 mmHg; the variance type for that overall contrast is not separately established, so CI=null. The −5.5 difference calculated from rounded arm means is descriptive, not a replacement causal estimate for the reported −5.6. [S01] |
|---|---|
| Evidence certainty | Confidence in the locked question is limited; not formal GRADE certification. |
| Applicability | This is not an effect for every hypertensive adult, every MTHFR genotype, or an exclusively treated subgroup. Participants were selected for TT from an older TUDA cohort without overt cardiovascular disease. [S01] |
| Safety | Trial-specific harm denominators and counts are unverified. General NIH consumer information is not evidence of zero events in this trial. Orange urine/tears in an NHS migraine leaflet is context at a different dose, not an observed outcome here. Caution does not mean harm was demonstrated. It separately marks incomplete trial harms reporting and long-term/special-population safety in the context of hypertension care. This page does not advise stopping, reducing or replacing antihypertensive therapy, self-diagnosing MTHFR genotype, or self-dosing riboflavin. The study dose is not personal dosing advice. [S01, S11–S13] |
The axes are B/S/R1/I1/E~/CX/B2. B is the claim type, not an efficacy grade B. No validated clinical threshold was verified, so magnitude was classified using a statistical convention: the reported between-group contrast divided by pooled baseline between-person SD is approximately−0.286. This is not an author-reported SMD, paired dz or validated MCID, and does not exclude clinical benefit. The unchanged calculator validates C; the zero-strength fixed anchor is46. [S01; supplied rubric cases28,45]
Useful facts when choosing a product
- The reported intervention is oral riboflavin1.6 mg/day for16 weeks. Administration count per day, exact chemical form, manufacturer, excipients and batch are unverified. It is not equated with FMN/FAD, multivitamins, injections or dietary exposure. [S01–S02]
- Baseline EGRac mean(SD) is1.37(0.26) with riboflavin and1.31(0.11) with placebo. Individual deficiency prevalence and total dietary intake are unverified; neither universal deficiency nor universal adequacy is inferred. [S01]
- Overall pill-count adherence was reported as99%; arm-specific values are unverified. Actual antihypertensive medication changes and regimen stability were not verified. [S01]
Chamgap Semantic Classification Code
Permanent code issued
S.riboflavin.oral-tablet-1-6mg-day-16weeks.adults-hypertension-mthfr677tt-no-overt-cvd-office-type-research-visit-sbp-16weeks.reduce.placebo-usual-background-careSubstances > Riboflavin (vitamin B2) > Oral tablet 1.6 mg/day for 16 weeks > Research-visit peripheral cuff SBP in hypertensive MTHFR 677TT adults > Reduce > Placebo plus usual background care
The reported between-group effect of −5.6 mmHg (P=0.033) is retained, while the exact CI and analyzed arm counts remain unverified; it is not relabeled as ambulatory/home BP, other genotypes or cardiovascular events. The code identifies the intervention and claim; it never contains the evidence grade, score, or safety result.
Exact Claim Classification
These independent facets prevent evidence from different forms, routes, populations, effects, and comparators from being mixed.
| Intervention class | S · Supplement or nutraceutical |
|---|---|
| Canonical ingredient or intervention | Riboflavin (vitamin B2), reported single-ingredient supplementation |
| Source or part used | Manufacturing origin and chemical certificate unverified; plant part not applicable |
| Formulation or processing | Reported ordinary riboflavin tablets; exact chemical form, excipients, release profile, product and batch unverified; not FMN/FAD or B-complex equivalence |
| Route | Oral, supported by registry instruction to take tablets and trial pill-box administration |
| Dose | 1.6 mg/day supplemental riboflavin; administration count, total diet and co-nutrient intake unverified |
| Duration | 16 weeks of supplementation; longer-term persistence unverified |
| Population | Adults with hypertension and MTHFR 677TT, without overt CVD, recruited from TUDA aging cohort; mean age 69.1 years; predominantly treated with a small untreated fraction; treated-only effect unverified |
| Effect or condition | Effect on investigator-measured research-visit peripheral cuff systolic blood pressure (office-type; exact physical site unverified), not general hypertension treatment, genotype screening or cardiovascular events |
| Primary endpoint | Investigator-measured research-visit peripheral cuff SBP treatment×time contrast at 16 weeks in mmHg (office-type; exact physical site unverified); not ambulatory, self-measured home series, central, daytime or nighttime SBP |
| Comparator | Placebo plus existing usual background care; medication changes and placebo matching details unverified |
| Duplicate-detection key | S|riboflavin-reported-ordinary-single|oral-tablet|1.6mg-day|16weeks|adult-older-TUDA-hypertension-MTHFR677TT-no-overt-CVD-predominantly-treated-mixed|research-visit-peripheral-cuff-SBP-office-type-site-unverified-change-mmHg-16weeks|placebo-usual-background-care|clinical-efficacy |
What the research actually shows
This is not an effect for every hypertensive adult, every MTHFR genotype, or an exclusively treated subgroup. Participants were selected for TT from an older TUDA cohort without overt cardiovascular disease. [S01] Among 91 randomized participants (46 riboflavin,45 placebo),3 dropouts were handled with LOCF and4 SBP outliers were excluded. The authors’ ITT label does not mean an unfiltered all-randomized analysis. Actual analyzed arm denominators, exact confidence interval, concealment implementation and prospective single-SBP hierarchy remain unverified. [S01–S02] Original Table3 mean(SEM) values are141.8(2.9)→137.1(3.0) with riboflavin and143.5(3.0)→144.3(3.1) mmHg with placebo. The reported overall reduction is5.6±2.6 mmHg; the variance type for that overall contrast is not separately established, so CI=null. The −5.5 difference calculated from rounded arm means is descriptive, not a replacement causal estimate for the reported −5.6. [S01]
Why this is classified as C (46)
The axes are B/S/R1/I1/E~/CX/B2. B is the claim type, not an efficacy grade B. No validated clinical threshold was verified, so magnitude was classified using a statistical convention: the reported between-group contrast divided by pooled baseline between-person SD is approximately−0.286. This is not an author-reported SMD, paired dz or validated MCID, and does not exclude clinical benefit. The unchanged calculator validates C; the zero-strength fixed anchor is46. [S01; supplied rubric cases28,45]
Counterpoint. Registration on2012-02-02 followed first recruitment on2010-05-01; the registered primary is broadly blood pressure. Governmental and DSM funding were mixed, with related patents and DSM-affiliated authors. These limitations are not converted into evidence of no clinical effect or fabrication. [S01–S02]
Rejudgment record. One directly eligible family; independent same-boundary replication unverified — Supplied rubric and unchanged calculator; tier2 statistical magnitude; zero-strength fixed anchor
| Endpoint | S | Surrogate marker - laboratory or imaging measures Case application: S: BP surrogate, not an event or patient-reported treatment goal. |
| Replication | R1 | Single confirmatory trial Case application: R1: one directly eligible randomized family, not an assertion of fully prospective confirmatory evidence. |
| Independence | I1 | Mixed funding sources |
| Effect size | E~ | Statistically positive but below the threshold |
| Precision | CX | No pooled confidence interval could be confirmed Case application: CX: CI unverified. Cohen convention is not used to exclude clinical benefit. |
Stored derived and displayed grades match; this is not a current recalculation or validity check (C).
Review performed and remaining limitations
The CI, between-group MCID and separate treated/untreated effects remain unverified. This is a completed current value, open to revision when new information appears. Single-assistant self-review is not independent external clinical peer review, journal certification or exhaustive-search assurance.
Preliminary RoB 2-informed review — not a complete formal assessment
| Randomization | SBP-stratified randomization reported; sequence generation and concealment implementation unverified. |
|---|---|
| Deviations from assigned interventions | Medication changes, maintained blinding and placebo matching incompletely verified. |
| Missing outcome data | LOCF for3 dropouts;4 SBP outliers excluded, not unfiltered ITT. |
| Outcome measurement | Same blinded researcher, A&D UA-787 and repeated cuff readings; exact physical site, posture and rest unverified. |
| Selection of the reported result | Retrospective registration, broad BP primary; prospective SAP and single-SBP hierarchy unverified. |
Reasons for the certainty judgment — not formal GRADE
| Risk of bias | B2: small sample, postrandomization exclusions and reporting gaps. |
|---|---|
| Inconsistency | No independent same-boundary replication verified; different populations and measurement types not forcibly pooled. |
| Indirectness | Restricted to TT, predominantly treated mixed cohort, older participants, office-type research visits and16 weeks. |
| Imprecision | Exact CI and between-group clinical threshold unverified. |
| Publication bias | Not quantitatively assessed; access limitations remain. |
Search scope and limitations. 53 general-web queries through2026-09-16;3 failed native search attempts; exact queries retained for reproducibility.
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| Wilson et al. 2013 targeted oral-riboflavin trial in hypertensive adults with MTHFR 677TT | SBP-stratified randomized placebo-controlled parallel trial; participant, BP-assessor and laboratory blinding reported; 16 weeks | 91 randomized (46 riboflavin, 45 placebo); LOCF for three dropouts and four SBP outliers excluded; actual analyzed arm denominators unverified | Mixed public/nonprofit and DSM support, with DSM-affiliated authors and related patent holders reported; authors stated funders had no role in design, conduct, analysis or interpretation | Investigator-measured research-visit peripheral cuff SBP at 16 weeks (A&D UA-787, repeated readings); office-type with exact site, posture and rest unverified; not ambulatory or home-series BP | Riboflavin 141.8 (SEM 2.9) to 137.1 (3.0), placebo 143.5 (3.0) to 144.3 (3.1) mmHg; reported between-group effect −5.6 mmHg, P=0.033; exact CI unverified | Only directly eligible family at the locked boundary; not generalized to all hypertension, other genotypes, treated-only effects, cardiovascular events or medication replacement |
Receipt — 20 References
Evidence access cutoff: 2026-09-16. Each citation states its actual access level (full-text transcription, abstract, index, or other) and remaining limitations. Bibliographic checking does not certify the study results or treatment efficacy.
Technical integration by: Codex · Evidence date: 2026-09-16 · Corrections: 1
Correction log — 1
Corrections applied to this verdict, in chronological order. Changes are logged, not erased.
- 2026-09-16 · Pre-delivery editorial corrections — Mixed treatment status, physical measurement site, SD/SEM, denominators, table conflicts, registration and trial linkage were explicitly corrected or retained. Prior verdicts were not changed.
Cite this verdict
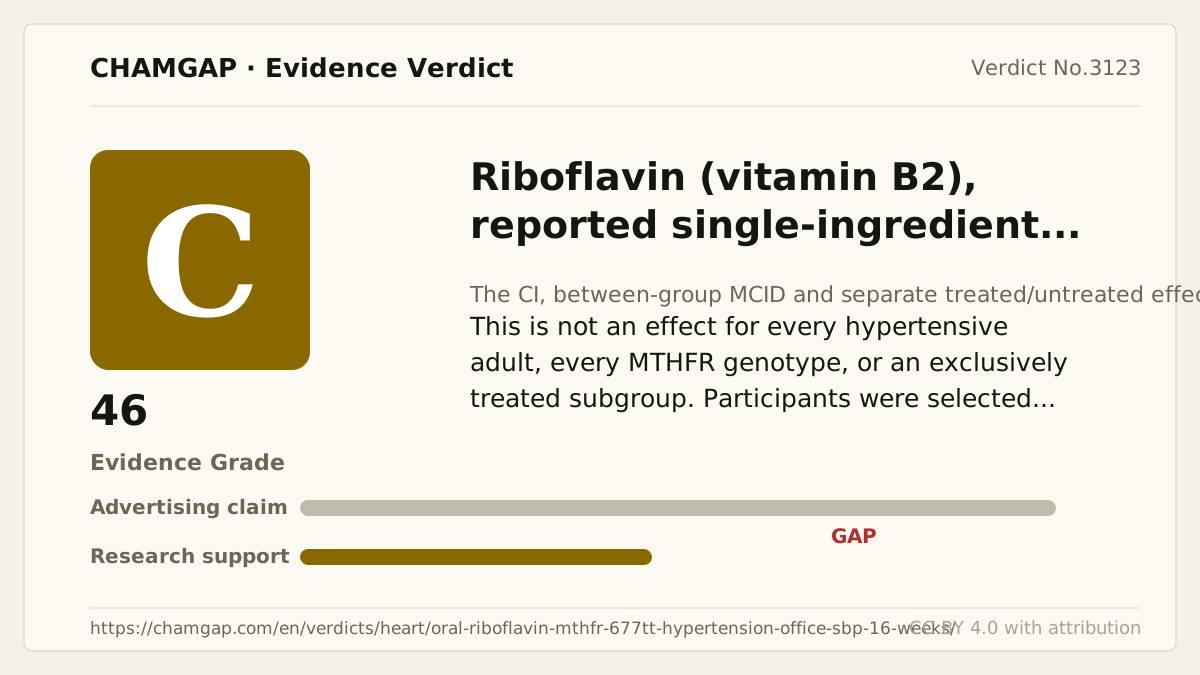
[Chamgap] Riboflavin and 16-week systolic blood pressure in MTHFR 677TT hypertension — Evidence Grade C·46. 20 cited sources checked. Source: https://chamgap.com/en/verdicts/heart/oral-riboflavin-mthfr-677tt-hypertension-office-sbp-16-weeks/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.