
Does adding folic acid 0.8 mg to common amlodipine treatment lower eight-week office systolic blood pressure?
research showsOn common amlodipine 5 mg, folic acid 0.8 mg gives an arithmetic eight-week/exit SBP change contrast of −3.2 mmHg. The official baseline-adjusted pairwise effect and CI are unverified; the three-arm P value is not the selected pairwise test. Additional SBP lowering is not established, but neither zero effect nor equivalence is established.
ads claimHomocysteine or stroke findings are not marketed as this SBP effect.
Four separate assessment dimensions
| Effect direction and size | On common amlodipine 5 mg, folic acid 0.8 mg gives an arithmetic eight-week/exit SBP change contrast of −3.2 mmHg. The official baseline-adjusted pairwise effect and CI are unverified; the three-arm P value is not the selected pairwise test. Additional SBP lowering is not established, but neither zero effect nor equivalence is established. |
|---|---|
| Evidence certainty | Actual axes B/S/R1/I2/EX/B1/CX produced C in the original calculator. This limited assessment reflects a surrogate and an unverified official adjusted effect, not efficacy success. |
| Applicability | Limited to Chinese hypertension, hyperhomocysteinemia and ACE-inhibitor intolerance, folic acid 0.8 mg added to common amlodipine 5 mg, and eight-week office SBP. Not generalized to confirmed deficiency treatment, normotension, other molecules/doses/background therapies or long-term events. |
| Safety | Caution: short-term trial safety is separated from official safety context. Organ-system AE rows are not summed as unique patients, and exact overall AE/SAE counts and long-term safety remain unverified. B12-deficiency masking and drug/population context require care; research doses are not personal dosing, prescription-change or discontinuation instructions. |
C/50 is a supplied rule-based index. Grade function C is distinct from the fixed numeric anchor: one public-funding I2 strength gives 50. It is not treatment-success probability, international GRADE or manuscript-quality scoring.
Useful facts when choosing a product
- The study used an oral amlodipine/folic-acid tablet; the additional active-ingredient difference is folic acid 0.8 mg.
- The entire study tablet is not described as folic-acid monotherapy; exact salts, excipients, batches and purity are unverified.
- Research doses are not personal dosing advice or instructions to change a prescription.
Chamgap Semantic Classification Code
Permanent code issued
M.folic-acid-0p8mg-added-amlodipine5mg.oral.chinese-htn-hhcy-acei-intolerance.8week-exit-office-sbp-mmhg.same-amlodipine5mg-no-added-folic-acidMedicines > Folic acid; the sole additional randomized active ingredient > Oral > Chinese adults with hypertension, hyperhomocysteinemia and ACE-inhibitor intolerance. Planned eligibility ages18–75; individual age range and diagnosed nutrient-deficiency count unverified. > Eight-week/exit office systolic BP in mmHg, mean of three readings; distinct from the trial composite primary endpoint. > Same amlodipine 5 mg/day without added folic acid and with placebo mimetics; exact other concomitant/rescue drugs unverified.
Original C/50, folic acid0.8mg added to common amlodipine, eight-week office SBP,43 uncertainties and both full reports preserved without regrading. The code identifies the intervention and claim; it never contains the evidence grade, score, or safety result.
Exact Claim Classification
These independent facets prevent evidence from different forms, routes, populations, effects, and comparators from being mixed.
| Intervention class | M · Medicine |
|---|---|
| Canonical ingredient or intervention | Folic acid; the sole additional randomized active ingredient |
| Source or part used | Manufacturing source, salt and crystal form unverified; distinct from dietary folate, 5-MTHF and folinic acid. |
| Formulation or processing | Amlodipine/folic-acid tablet and two placebo mimetics with matching appearance; release, excipients, lots and purity unverified. |
| Route | Oral |
| Dose | Folic acid 0.8 mg/day plus common amlodipine 5 mg/day, once daily; total nutritional intake unverified. |
| Duration | Eight weeks after randomization / exit analysis; run-in details and individual actual final-measurement timing unverified. |
| Population | Chinese adults with hypertension, hyperhomocysteinemia and ACE-inhibitor intolerance. Planned eligibility ages18–75; individual age range and diagnosed nutrient-deficiency count unverified. |
| Effect or condition | Additional SBP reduction on common amlodipine |
| Primary endpoint | Eight-week/exit office systolic BP in mmHg, mean of three readings; distinct from the trial composite primary endpoint. |
| Comparator | Same amlodipine 5 mg/day without added folic acid and with placebo mimetics; exact other concomitant/rescue drugs unverified. |
| Duplicate-detection key | folic-acid|oral-drug-tablet|0.8mg-day|amlodipine5mg-common|chinese-hypertension-hyperhomocysteinemia-ACEI-intolerance|office-SBP-three-readings|8week-exit|same-amlodipine-no-added-folic-acid |
What the research actually shows
# Does adding folic acid 0.8 mg to common amlodipine treatment lower eight-week office systolic blood pressure?
**TASK-1043 / R01-083 · New independent claim · Evidence snapshot: 2026-09-17T20:22:51+09:00**
## Thirty-second answer
A Chinese trial in hypertension, hyperhomocysteinemia and ACE-inhibitor intolerance compared folic acid 0.8 mg/day added to amlodipine 5 mg/day with the same amlodipine dose without added folic acid. Mean SBP changes in the eight-week/exit analysis were −16.8 and −13.6 mmHg. Their **simple arithmetic difference was −3.2 mmHg**. This is not the paper's official baseline-adjusted between-group estimate. The selected pair's official adjusted coefficient, confidence interval and P value were not verified; the table's P=0.147 compares three groups. Thus, **additional SBP lowering is not established within this selected scope**. Neither zero effect, equivalence nor ineffectiveness in every hypertensive population has been established. [S01]
The efficacy-evidence assessment is **C / 50 points** under the supplied rules. The surrogate-endpoint ceiling and EX(a), reflecting the unverified official adjusted effect, apply. This is not a treatment-success probability or an international GRADE rating. The safety label is **Caution**. Manuscript quality is **A, assessed by the same model**. These are separate judgments.
## 1. The question and the actual trial boundary
This page evaluates the randomized incremental contrast in a drug trial. The intervention tablet contains both amlodipine and folic acid, but both selected groups receive amlodipine 5 mg; therefore, **the additional active-ingredient difference is folic acid 0.8 mg**. This is not a trial of folic acid alone without antihypertensive treatment. The actual drug-trial formulation supports kind **M, medicine**, while the canonical list ingredient is **Folic acid** and the task module remains R01/NUT. This classification does not establish a blood-pressure indication approval or equivalence to a marketed product. [S01] [P02]
| Selected dimension | Adopted scope | |---|---| | Population | Adults in a Chinese trial of hypertension, hyperhomocysteinemia and established ACE-inhibitor intolerance. The protocol abstract describes eligibility at ages 18–75 with mild-to-moderate hypertension; actual individual age limits and full diagnostic records were not verified | | Added molecule | Reported folic acid 0.8 mg/day, distinct from 5-MTHF, folinic acid, dietary folate, fortified food and combined B vitamins | | Common treatment | Reported amlodipine 5 mg/day; its salt is not inferred from usual commercial products | | Actual comparison | Group B: amlodipine 5 mg/folic acid 0.8 mg tablet; group C: amlodipine 5 mg tablet. Each also took two placebo mimetics of the other treatments | | Route and duration | Oral, once daily, eight weeks after randomization. Actual run-in dose/duration and total nutritional intake remain unverified | | Primary measurement method | Office BP at 8–10 am, right arm supported at heart level, after five minutes seated; average of three readings 30 seconds apart | | This page's primary endpoint | Eight-week/exit SBP in mmHg. Lower values represent lower BP. Exit analyses may include last-observation imputation | | Separate outcomes | DBP, pulse pressure, categorical BP response, homocysteine, vascular function, stroke/cardiovascular events, home and 24-hour ambulatory BP |
The 0.8-mg pair was selected because it isolates the additional active ingredient against common treatment and provides SBP means, denominators, dispersion and timing. This is an **editorial primary comparison selected after reviewing the literature**, not a retrospective claim that it was the trial's original registered primary contrast. The same trial's 0.4-mg arm is a dose-boundary comparison, not another completed task or independent replication. [S01] [S02] [S03]
## 2. Reuse and exact-duplicate assessment
The supplied 3,158-record index was searched for names and synonyms. The ten complete candidate JSON records and the thirteen selected original files for each of records 3107–3110 were compared with their handoff identities. **No exactly matching completed claim was identified.** An automatic entity-and-endpoint text match is not duplicate confirmation.
In record 3107, hypertension defines the population, while the completed claim is prevention of first symptomatic stroke. Its full manuscript uses follow-up-average BP to describe background treatment, not as a separately completed assessment of this eight-week SBP contrast. The CSPPT trial-family map, extractions, searches and safety context were reused without transferring its stroke grade C/56 or average follow-up BP into the present effect estimate. Record 3108 concerns deficient anemia and hemoglobin, 3109 concerns BDI-II in major depressive disorder, and 3110 concerns sperm motility in male infertility. [P01]
Record 121 is a legacy mixed-health claim; 486 and 1059 use other combined B vitamins; 1690 concerns adenoma recurrence; and 1133 concerns a folate-receptor-targeted anticancer medicine. **Site record 1043 concerns methotrexate in rheumatoid arthritis and is a different identifier from TASK-1043.** Additional index matches 3088, 3112, 3113, 3146 and 398 concern other ingredients, molecular forms or endpoints. Their complete originals were not supplied and are not represented as read.
Reused IDs are **121 / 486 / 1043 / 1059 / 1133 / 1690 / 3107 / 3108 / 3109 / 3110**. The complete old archives for 3107–3110 were not provided: only thirteen selected original files per record were supplied and preserved. `publication.ko.md`, `publication.en.md` and `research_report.md` remain distinct exact files. Historical predeployment manifest states and the forwarded Korean filename alias for task 78 remain unchanged.
## 3. Direct trial: design, intervention and nutritional status
Bao and colleagues' 2023 report describes NCT01956786, a four-center randomized, double-blind, parallel-group drug trial. Reported conduct ran from December 19, 2013 to March 6, 2014; the final article was first published on July 11, 2023. Publication year is not treatment year. The protocol, final report and author-shared copy belong to one trial family. [S01] [S02] [S09] [S11]
A total of 360 people were randomized, 120 per arm. Nine eligibility errors were excluded, leaving a full analysis set, or FAS, of 351. The selected B and C groups have 118 and 117 analyzed participants, respectively, not 120 each. The abstract's wording about 351 randomized people was not used to replace the flow-based randomized count. The FAS definition also excludes people without any postrandomization follow-up record; primary efficacy missing data were handled with last observation carried forward, or LOCF. The exact SBP imputation count and last-observation timing were not verified. Exit means are not guaranteed to be observed week-eight measurements for everyone. [S01] (§2.7, §3.1–3.2)
For groups B/C, mean age was 62.9 (SD 5.9)/63.2 (SD 6.5) years and male counts were 37/118 and 35/117. Baseline serum folate medians were 10.9 (IQR 8.6–14.1)/10.7 (8.0–13.8) ng/mL; mean eGFR was 89.0 (SD 12.6)/89.9 (SD 12.7) mL/min/1.73 m². These summaries establish neither that everyone had adequate intake nor that everyone had diagnosed folate deficiency. Baseline B12, deficiency counts and total dietary/fortified-food intake were not verified. [S01] (Tables 1–2)
Exact manufacturing source, salts, crystal forms, release characteristics, lots, purity and excipient compositions remain unverified. The report states that the three pills matched in appearance, size, color and taste; this is not expanded into a chemical-equivalence validation. The Beckman Coulter instrument used for serum folate analysis was not incorrectly assigned as the BP-device model. [S01] (§2.1, §2.3–2.4)
## 4. Main numbers: reported data versus arithmetic
**The following values are means and SDs from Table 2, not SEs.**
| SBP item, mmHg | B: amlodipine 5 mg + folic acid 0.8 mg | C: amlodipine 5 mg | Interpretation | |---|---:|---:|---| | FAS | 118 | 117 | Distinct from 120 randomized per arm | | Baseline mean (SD) | 150.8 (7.6) | 149.8 (8.6) | Arithmetic baseline difference B−C: +1.0 | | Exit mean (SD) | 134.0 (13.4) | 136.2 (12.0) | Arithmetic exit difference B−C: −2.2 | | Reported reduction, baseline minus exit, mean (SD) | 16.8 (12.6) | 13.6 (13.3) | A positive value denotes reduction | | Change expressed here as exit minus baseline | −16.8 | −13.6 | Sign conversion only; within-group changes | | Arithmetic change contrast, B−C | **−3.2** | — | Calculated value, not the official adjusted coefficient |
The reported three-group P values are 0.147 for change, 0.118 for percentage reduction and 0.407 for exit values. None is labelled here as the selected B-versus-C pairwise P value. The paper describes a three-group Kruskal–Wallis comparison because of skewed distributions, followed by baseline-covariate ANCOVA to obtain least-squares means, SEs and between-group CIs. However, the **official adjusted continuous-SBP coefficient, SE and CI for the selected pair** were not verified in the accessible main report. [S01] (§2.7, Table 2)
The calculated −3.2 equals `(134.0−150.8)−(136.2−149.8)`. It differs from the exit contrast of −2.2. The larger within-group reduction of −16.8 is not attributed to adding folic acid. An ANCOVA approximation reconstructed from rounded marginal summaries would require assumptions about common analysis membership, covariance and imputation; it would not become an official reported estimate. No official CI was manufactured without raw data or verified exact reconstruction conditions. A validated between-group MCID was not obtained, and the trial's individual BP-response criterion involving a 30-mmHg SBP reduction was not repurposed as one.
## 5. Primary endpoint, missingness, adherence and multiplicity
The trial's primary result is **a response combining reductions in homocysteine and BP**, not continuous SBP alone. The higher composite response and the article title do not establish superiority for SBP alone. The categorical BP-response endpoint also combines mainly DBP criteria with some SBP criteria and differs from this page's continuous SBP change. [S01] (§2.5, Tables 2–3)
Power calculations concerned the composite response and described a Bonferroni threshold of α<0.025. This does not verify multiplicity adjustment for every secondary or continuous-SBP comparison. The initial registry, version history, signed SAP and inaccessible supplementary file were not represented as read. The trial number was corroborated, but the original registration priority of continuous SBP remains unverified. [S01] [S02] [S03] [S10] (§2.7; access limits)
At least 80% adherence was reported in 115/120 participants in B (95.8%) and 112/120 in C (93.3%). Those denominators are not the FAS denominators of 118/117. Overall loss to follow-up was 22/360 (6.1%), including nine in B and five in C. Some people were followed after discontinuing assigned treatment; stopping medication is therefore not identical to loss to follow-up. Individual cumulative exposure remains unverified. [S01] (§3.2)
Advice to keep usual diet and avoid other B-vitamin supplements does not verify total intake. The paper's wording about avoiding antihypertensive medications must be read alongside the assigned amlodipine intervention; ambiguous wording was not silently repaired into a claim that all concomitant drugs were identical. Screening antihypertensive use was reported for 114/118 in B and 110/117 in C, but subsequent drug-specific exposure, rescue medication, alcohol and dietary changes were not sufficiently separated. [S01] (§2.1, Table 1)
The narrative says all baseline comparisons had P>0.05, whereas Table 2 reports baseline DBP P=0.040. Both are retained. This does not establish a statistically significant SBP imbalance; the selected baseline SBP arithmetic difference is +1.0 mmHg. Conflicting source statements were not repaired with invented replacement values.
## 6. Other directly relevant and contrary evidence
### Different dose and population: Sharifi et al. 2010
An Iranian trial of folic acid 5 mg/day versus placebo for six weeks reports 42 participants and 37 completers, 18/19 by arm. The report describes hypertensive, hyperhomocysteinemic participants, seated mercury-sphygmomanometer measurements and four existing antihypertensive users in each group. Complete background-drug types and doses were not verified. [S04]
Table 2 reports baseline-to-exit SBP of 148.2→128.1 versus 146.3→143.0 mmHg. The arithmetic change contrast is −16.8 mmHg, a positive adjacent finding. However, reported change SDs of 1.70 and 0.10, a baseline SD elsewhere and narrative/table sex counts leave internal concerns. These concerns are neither declared proven measurement error or fabrication nor used to generate a highly precise CI or standardized effect from questionable dispersion values. A 5-mg, six-week, differently treated population was not pooled with the 0.8-mg, eight-week, common-amlodipine contrast. [S04] (Table 2; visual PDF-table check)
### Mixed meta-analyses and long-term stroke evidence
Long and colleagues' 2026 review maps trials with searches through October 2024 across doses, baseline conditions, molecular forms and comparators. A 2026 publication date does not imply that every trial through 2026 was searched. Its pooled standardized value is not the fixed contrast in mmHg assessed here, and inclusion of Bao's trial in a review does not add independent replication. The broad Asbaghi review estimate is likewise not the authoritative estimate for the selected pair. [S05] [S06]
CSPPT was reused as the stroke-trial family already assessed in record 3107. Average on-treatment BP, stroke hazard ratios, studies in normotensive smokers or healthy people, folic acid combined with B6/B12, 5-MTHF or folinic acid, dietary observations and animal mechanisms were not converted into the present SBP effect. Human-study existence, direct eligibility for this narrow question and source-access level are separate information states. [P01] [S05] [S06]
## 7. Actual grade derivation and score adoption
The supplied rubric and original grade calculator were executed here without modifying the calculator. Its SHA was unchanged, `validate_axes=[]`, `derive_grade=C`, `check_verdict=[]`, and CLI exit code was 0. Four JSON receipts preserve the input, raw output, execution and final adoption in `grading/`. The calculator is **a grade function, not an automatic numerical-score validator**. The 50-point score comes from a separate application of the supplied fixed-anchor table. [P03]
| Axis | Adopted value | Evidence and scope | |---|---|---| | Claim | B | Clinical add-on BP efficacy | | Endpoint | S | Office SBP surrogate; ceiling C | | Replication | R1 | One directly applicable trial family for the selected scope; not a claim of preregistered SBP success or independent multiple replication | | Independence | I2 | National, regional public and hospital support explicitly verified in the funding/conflict sections; not certification of every product or contract relationship | | Effect | EX(a) | Case 30: the official baseline-adjusted SBP contrast and precision are unverified; arithmetic is not the official estimate | | Bias | B1 | Actual duration is eight weeks, below 12; unknown funding, CI or concealment is not invented as an additional defect | | Precision | CX | The selected official between-group CI is unverified; neither exclusion of benefit nor equivalence |
Directly confirmed public support supplies one I2 strength. R1, S, EX, B1 and CX do not supply the other fixed-anchor strengths. The **C-band anchor for one strength is 50**. The code-derived and adopted grades agree, so there is no grade override. The legacy E0 label was not mechanically assigned from a nonsignificant three-group P value. Bilingual `axis_notes` also explain that the legacy R1 phrase “confirmatory trial” does not mean statistical success for this SBP endpoint.
Public support was affirmatively reported in the primary source. A company-sponsor listing surfaced in a secondary registry mirror and remains a separate lead. Without the complete official registry, sponsor was not transformed into a monetary funding source or a manufacturer-only evidence claim. I2 classifies the disclosed trial support under the supplied rules; it does not verify all undisclosed contracts. New original funding or product-control information that changes this assessment would trigger a traceable axis/score revision. [S01] [S03] (funding/conflicts; registry access limitation)
## 8. Safety: Caution
The trial's safety table uses 120 participants per group. Organ-system AE rows were not summed into unique patients with any AE or an overall AE rate. The narrative's nonsignificant AE comparison does not establish safety equivalence or zero harm. Exact unique AE counts, SAE counts, AE-related discontinuations and long-term or special-population safety remain unverified. [S01] [S10] (Table 4)
Official nutritional information and a separate product document caution that folic acid may improve the anemia of B12 deficiency while recognition of neurological problems is delayed. Antiseizure medicines and methotrexate require drug- and indication-specific interpretation. Warnings, excipients and frequencies for that separate 5-mg product were not transferred into direct facts about this 0.8-mg trial product. Pregnancy, lactation, children, severe renal/hepatic disease, deficiency treatment and supplementation in adequately nourished adults remain separate boundaries. [S07] [S08]
**Research doses and comparisons here are not personal dosing advice, prescription changes, instructions to stop medication or substitutes for standard antihypertensive treatment.** They do not instruct anyone to independently alter clinician-agreed BP treatment or assessment.
## 9. Access, manuscript quality and revision conditions
Source verification used public web search, publisher HTML, the adjacent trial's PDF and visual tables, official safety documents and supplied prior extractions. No exhaustive subscription-database search, complete registry version audit, review of all supplements, individual records, contracts or Crossmark entries was performed. Some downloads and supplementary-file requests failed; unavailable files and their hashes were not invented. Access levels and locations are in `sources.json`; routes are in `research/search_log.json`; numerical extraction and calculations are in `research/numeric_evidence.json` and `research/arithmetic_receipt.json`.
All 115 input files were read as bytes and UTF-8, with JSON parsing and identity checks where applicable. Only the supplied historical originals were reused; complete old archives were not claimed recovered. Each full Korean/English report exactly matches that language's `body_markdown` and `what_research`. No original `what_research` for this new task was supplied, so the original-value field remains null with a reason; the input question is separately preserved in its original bytes.
Manuscript quality **A** is the same model's assessment of source traceability, numbers, boundaries, uncertainty, bilingual completeness and format. It is separate from efficacy C/50 and is not independent external review, journal certification or an error-free guarantee. Translation, copies of the same paper, archive restoration and regression tests are not independent clinical replication.
The result is `completed_with_uncertainty`, content verification is `completed_with_declared_scope`, and editorial readiness is `ready_with_uncertainty`. New ID, slug, URL, semantic code and first-publication date remain unassigned null; technical publication status is `needs_id_assignment`. `clinical_todo=[]`: content assessment is completed here. Exact official adjusted SBP and CI, registry history, product/funding documents, directly matching new trials, corrections/retractions or evidence changing the judgment would trigger a tracked revision retaining the eventual publication ID.
The current chat's previously completed FULL items are 79–82. This task 83 supplies the fifth content-and-attachment handoff, but **server integration, deployment and HTTP checks for this task were not performed here**. Task 84 was not started.
## Source links
[S01]: https://onlinelibrary.wiley.com/doi/full/10.1111/jch.14697 [S02]: https://www.ovid.com/jnls/pn/fulltext/10.1097/pn9.0000000000000019~a-multicentered-randomized-double-blind-parallel-controlled [S03]: https://clinicaltrials.gov/study/NCT01956786 [S04]: https://jdmd.tums.ac.ir/index.php/jdmd/article/download/251/21 [S05]: https://link.springer.com/article/10.1186/s40795-026-01343-y [S06]: https://pureportal.coventry.ac.uk/en/publications/folic-acid-supplementation-and-blood-pressure-a-grade-assessed-sy/ [S07]: https://ods.od.nih.gov/factsheets/Folate-HealthProfessional/ [S08]: https://www.medicines.org.uk/emc/product/14604/smpc [S09]: https://www.researchgate.net/publication/372287338_Combined_use_of_amlodipine_and_folic_acid_are_significantly_more_efficacious_than_amlodipine_alone_in_lowering_plasma_homocysteine_and_blood_pressure_among_hypertensive_patients_with_hyperhomocysteine [S10]: https://onlinelibrary.wiley.com/doi/suppl/10.1111/jch.14697/supinfo/jch14697-sup-0001-SuppMat.docx [S11]: https://pubmed.ncbi.nlm.nih.gov/37433173/ [P01]: audit/duplicate_boundary.json [P02]: reference/input/%EC%B0%B8%EA%B3%A0%EC%9E%90%EB%A3%8C/%EB%8B%A4%EB%A9%B4%EB%B6%84%EB%A5%98-v1.md [P03]: grading/final_adoption_receipt.json
Why this is classified as C (50)
C/50 is a supplied rule-based index. Grade function C is distinct from the fixed numeric anchor: one public-funding I2 strength gives 50. It is not treatment-success probability, international GRADE or manuscript-quality scoring.
Counterpoint. 148.2→128.1 versus 146.3→143.0; arithmetic change contrast −16.8. Internal SD and sex-count concerns retained; official CI unverified.
Rejudgment record. Original calculator and adopted grade agree; not independent external review. — Actual axes B/S/R1/I2/EX/B1/CX produced C in the original calculator. This limited assessment reflects a surrogate and an unverified official adjusted effect, not efficacy success.
| Claim type | B | B: a clinical add-on efficacy claim for blood pressure. |
| Endpoint | S | Surrogate marker - laboratory or imaging measures Case application: S: office SBP is a surrogate, not stroke or mortality. |
| Replication | R1 | Single confirmatory trial Case application: R1 denotes one directly applicable trial family for the selected 0.8-mg, common-amlodipine, eight-week contrast. The legacy phrase confirmatory trial does not assert statistical success or a preregistered primary continuous-SBP endpoint. |
| Independence | I2 | Decisive evidence is publicly or non-profit funded Case application: I2 follows public and hospital support explicitly reported in the primary funding and conflict sections. It is not inferred from failure to find industry support. A secondary registry mirror company-sponsor listing was not adopted as funding evidence; complete product and contract independence is not guaranteed. |
| Effect size | EX | The clinical size of the effect could not be judged Case application: EX(a): arithmetic table contrasts exist, but the report describes baseline-adjusted ANCOVA. The selected official adjusted coefficient, SE and CI were not available and exact reconstruction conditions were unverified, so Case 30 applies. EX was not assigned solely because an MCID is unavailable, and does not mean E0, equivalence or zero effect. |
| Precision | CX | No pooled confidence interval could be confirmed Case application: CX: the official selected between-group CI is unverified. A three-group P value does not establish exclusion of benefit or equivalence. |
| Risk of bias | B1 | B1 counts the actual eight-week duration below 12 weeks. The selected FAS has 235 people, above 200; overall 6.1% loss is below 15%. Postrandomization eligibility exclusions and LOCF limitations remain explicit, without inventing additional concealment defects or double-counting funding and CI uncertainty. |
Review performed and remaining limitations
The official adjusted effect, CI, pairwise P, MCID, registry history and some formulation, concomitant-exposure, imputation and safety details remain unverified. Denominator/baseline-DBP reporting conflicts and adjacent 5-mg-trial dispersion concerns remain explicit.
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| S01/S09/S11 · Bao 2023 · one NCT01956786 trial family | Randomized, double-blind, three parallel arms; B versus C selected here, with continuous SBP separate from the composite primary endpoint. | Overall randomized 360, FAS 351; selected B/C randomized 120/120 and FAS 118/117. | National, regional public and hospital support confirmed in primary funding/conflict sections; complete product/contract details unverified. | Eight-week/exit office SBP in mmHg, three right-arm readings averaged; exact LOCF details unverified. | Baseline 150.8/149.8; exit 134.0/136.2; arithmetic change contrast −3.2. Official adjusted effect, CI and selected pairwise P are null. | One selected direct trial family. The 0.4-mg arm, composite response, copies and protocol add no independent replication. |
| S02/S03/S10 · same-trial protocol, registration and supplement | Protocol abstract/index and official registry shell; full history and supplement inaccessible. | Planned 360 is not substituted for actual completers; actual denominators link to S01. | Separate original product/funding contracts unverified; planned and actual facts remain separate. | Reported primary plan combines homocysteine and BP response; original continuous-SBP registration priority unverified. | The common trial identifier was verified. Unread adjusted effects, CIs and historical registry results were not invented. | Design/access context for the same trial, adding zero independent replications. |
| S04 · Sharifi 2010, Iranian 5-mg trial | Folic acid 5 mg/day versus placebo for six weeks in hypertension/hyperhomocysteinemia; different background treatment. | 42 participants and 37 completers, 18/19; complete randomized arm and loss flow unverified. | University research-center support reported; not transferred as funding of the selected main trial. | Six-week seated mercury-sphygmomanometer SBP, mmHg; separated from the eight-week method and comparison. | 148.2→128.1 versus 146.3→143.0; arithmetic change contrast −16.8. Internal SD and sex-count concerns retained; official CI unverified. | Positive adjacent evidence with different dose, time, population and background drugs; not pooled or counted as directly matching R2. |
| S05/S06 · Long 2026 and Asbaghi review maps | Systematic maps spanning conditions, doses, molecular forms and comparators. | Review totals are not added as independently randomized participants for this question. | Review-institution independence does not substitute for primary-trial funding. | Pooled BP and nutrient markers, sometimes standardized effects; not the fixed B-versus-C mmHg contrast. | Mixed pooled values are not substituted for 0.8 mg, eight weeks and common amlodipine. | Discovery and boundary checks; no duplicate counting of the same underlying trial. |
| Provided record 3107 · reused CSPPT extraction | Long-term first-stroke trial of folic acid added to common enalapril treatment. | 20,702 in the original supplied record; not added as directly replicated participants for this SBP claim. | Existing mixed-funding record preserved, not transferred to Bao. | First symptomatic stroke; follow-up-average BP describes common management. | Existing stroke C/56 retained. Its grade, hazard ratio and average BP are not used as the present eight-week SBP effect. | Duplicate prevention, trial-family and safety reuse; only thirteen selected original files were supplied. |
Receipt — 12 References
Evidence access cutoff: 2026-09-17. Each citation states its actual access level (full-text transcription, abstract, index, or other) and remaining limitations. Bibliographic checking does not certify the study results or treatment efficacy.
Technical integration by: Codex · Evidence date: 2026-09-17 · Corrections: none
Cite this verdict
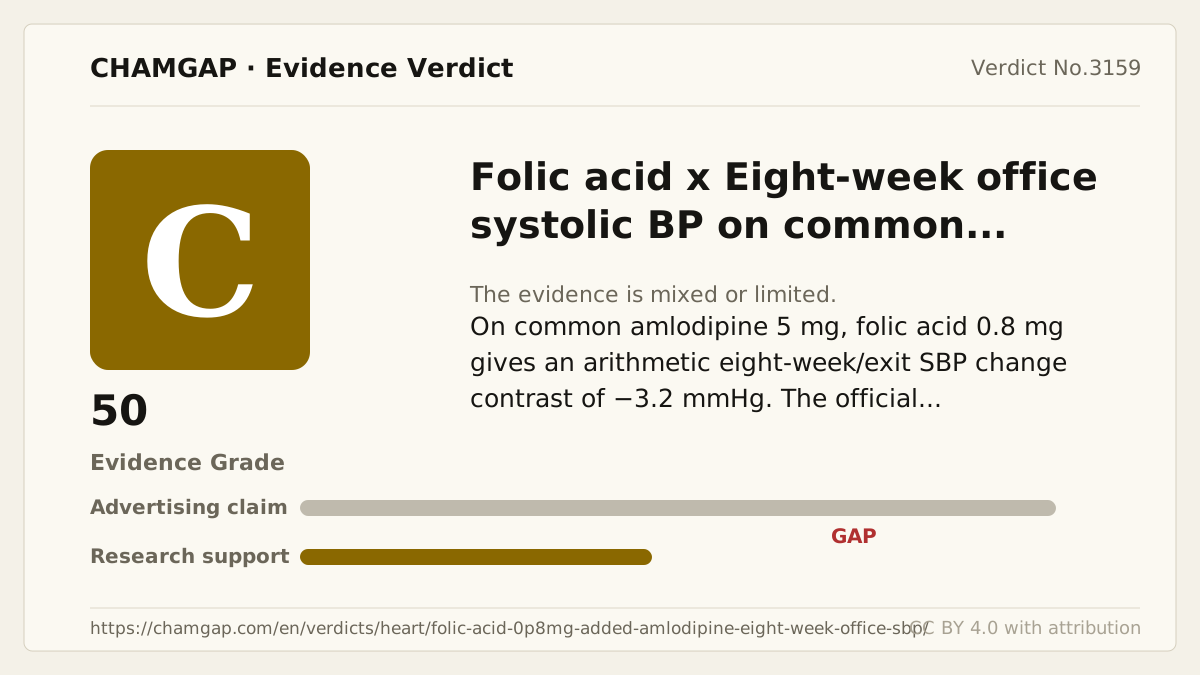
[Chamgap] Does adding folic acid 0.8 mg to common amlodipine treatment lower eight-week office systolic blood pressure? — Evidence Grade C·50. 12 cited sources checked. Source: https://chamgap.com/en/verdicts/heart/folic-acid-0p8mg-added-amlodipine-eight-week-office-sbp/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.