
Prophylactic platelet transfusion,
does it really help with Reduced grade 2-to-4 procedure-related bleeding within 24 hours?
research showsThe grade is B. PACER randomized 411 CVC placements; 393 entered the intention-to-treat population and 373 the per-protocol analysis. In the 373 per-protocol procedures, grade 2-to-4 bleeding occurred in 9/188 (4.8%) with transfusion versus 22/185 (11.9%) without transfusion; the no-transfusion versus transfusion RR was 2.45 (90% CI 1.27 to 4.70), and the absolute difference was 7.1 points (90% CI 1.3 to 17.8). The no-transfusion margin was a 2.5-point absolute increase or a relative-risk upper confidence bound of 3.5, and noninferiority was not met. One publicly funded noninferiority trial gives B with 72 points.
ads claimThis result applies to one preprocedure platelet unit before ultrasound-guided CVC placement in adults with counts of 10,000 to 50,000 per microliter. It cannot be generalized to every invasive procedure, platelet count, or non-ultrasound insertion.
Useful facts when choosing a product
- Every CVC was placed under ultrasound guidance by an operator with at least 50 prior placements, and bleeding was assessed through 24 hours.
- The prespecified no-transfusion margin was a 2.5-point absolute increase in bleeding and a 90% RR confidence-bound threshold of 3.5.
- Verdict 2532 is B with 76 points for a lower platelet-transfusion threshold in premature infants; this verdict concerns adult pre-CVC prophylaxis, a different population and intervention.
Chamgap Semantic Classification Code
Candidate index · review held
UNK.one-unit-of-prophylactic-platelet-concentrate-before-ultrasound-guided-cvc-placement-in-adults-with-10.intravenous.grade-2-to-4-procedure-related-bleeding-within.reduce.UNKUnknown > One unit of prophylactic platelet concentrate before ultrasound-guided CVC placement in adults with 10 > Intravenous > grade 2-to-4 procedure-related bleeding within > Reduction claim > Unknown
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
van Baarle FLF, van de Weerdt EK, van der Velden WJFM, Ruiterkamp RA, Tuinman PR, Ypma PF, van den Bergh WM, Demandt AMP, Kerver ED, Jansen AJG, Westerweel PE, Arbous SM, Determann RM, van Mook WNKA, Koeman M, and colleagues randomized 411 CVC-placement episodes at 10 Dutch hospitals. Eighteen were excluded after consent refusal, withdrawal, or related reasons, leaving 393 in the intention-to-treat population; a further 20 protocol violations were excluded from the 373-placement per-protocol analysis. Primary-outcome missingness was 7.2%, and multiple-imputation and intention-to-treat sensitivity analyses were directionally consistent. ZonMw grant 843002625 funded the trial.
Why this is classified as B (72)
A publicly funded multicenter trial found fewer prespecified bleeding events with transfusion, and no-transfusion noninferiority failed. One noninferiority trial gives B with 72 points.
Counterpoint. The major-bleeding-only interval was wide. Site, catheter type, bleeding risk, and transfusion harms all matter in individual decisions.
Rejudgment record. Cross-check applied — The article, protocol, and registry were cross-checked for noninferiority direction and margin, primary endpoint, actual primary-analysis procedures, missing-data handling, bleeding counts, and public funding.
| Endpoint | H | Hard endpoint - actual events such as death |
| Replication | R1 | Single confirmatory trial |
| Independence | I2 | Decisive evidence is publicly or non-profit funded |
| Effect size | E+ | Meets the clinically important threshold |
Stored derived and displayed grades match; this is not a current recalculation or validity check (B).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Reduced grade 2-to-4 procedure-related bleeding | B | Rates were lower with transfusion, 4.8% versus 11.9%. |
| Reduced grade 3-to-4 major bleeding | D | The 95% interval around RR 2.43 included 1. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| van Baarle FLF, van de Weerdt EK, van der Velden WJFM, Ruiterkamp RA, Tuinman PR, Ypma PF, van den Bergh WM, Demandt AMP, Kerver ED, Jansen AJG, Westerweel PE, Arbous SM, Determann RM, van Mook WNKA, Koeman M et al., 2023 PACER | Multicenter open-label randomized noninferiority trial | 411 CVC placements randomized; 393 in the intention-to-treat population; 373 per-protocol placements in 338 patients, 188 and 185 | Public ZonMw grant 843002625 | Grade 2-to-4 CVC-related bleeding within 24 hours | Transfusion 9/188 (4.8%) versus no transfusion 22/185 (11.9%); no-transfusion versus transfusion RR 2.45 (90% CI 1.27 to 4.70), absolute difference 7.1 points (90% CI 1.3 to 17.8) | Single publicly funded bleeding-event noninferiority trial |
Receipt — 2 References
All 2 cited sources were verified for existence at the original page (as of 2026-08-14).
Final verification and publication gate: Codex · Evidence date: 2026-08-14 · Corrections: none
Cite this verdict
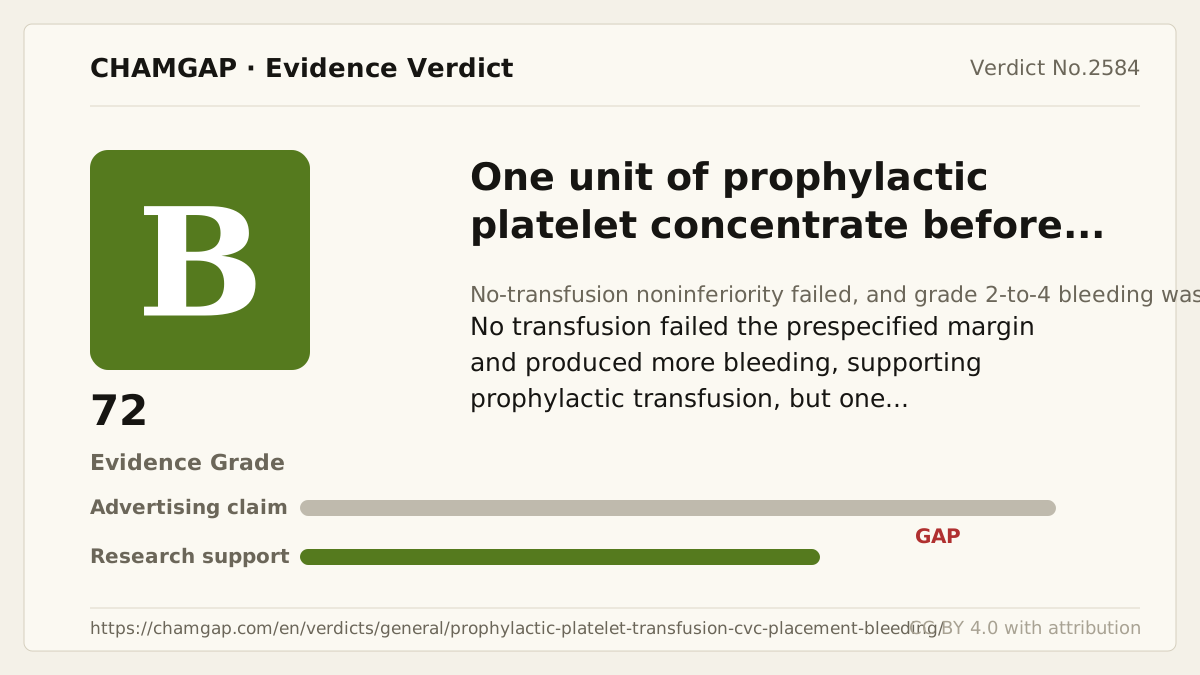
[Chamgap] Prophylactic platelet transfusion x bleeding after CVC placement — Evidence Grade B·72. 2 cited sources checked. Source: https://chamgap.com/en/verdicts/general/prophylactic-platelet-transfusion-cvc-placement-bleeding/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.