
Frequent higher-dose mobilisation within 24 hours after stroke,
does it really help with Increase in favorable three-month functional outcome, modified Rankin Scale 0 to 2?
research showsThe grade is D. AVERT randomized 2,104 patients and analyzed 2,083 at three months. Favorable outcome occurred in 480/1,038 (46.2%) versus 525/1,045 (50.2%), adjusted OR 0.73 (95% CI 0.59 to 0.90), P=0.004, significantly worse with the intervention. A large independent trial contradicted the benefit claim, but this was not repeated refutation of the same regimen, so the result is D, not F, with 34 points.
ads claimMarketing cannot isolate only 'moving early.' AVERT tested a package combining start within 24 hours with greater session frequency and total dose than usual care.
Useful facts when choosing a product
- Ninety-two percent of intervention patients and 59% of usual-care patients first mobilized within 24 hours.
- Randomization assigned 1,054 versus 1,050 patients.
- The favorable-outcome analysis included 1,038 versus 1,045.
Chamgap Semantic Classification Code
Candidate index · review held
UNK.frequent.UNK.favorable-functional-outcome-modified-rankin-scale-0-to-2.increase.usual-careUnknown > Frequent > Unknown > favorable functional outcome, modified Rankin Scale 0 to 2 > Increase claim > Usual care
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
Across 56 units in five countries, baseline data were entered before centralized web-based computer block randomization. Patients, three-month outcome assessors, and data-management investigators were masked, and 2,083/2,104 (99%) were analyzed by allocation. The registered and published three-month mRS 0 to 2 primary endpoint matched. Funding came from NHMRC, Singapore Health, stroke charities in the UK, Scotland and Northern Ireland, and NIHR.
Why this is classified as D (34)
One rigorous independent trial significantly worsened a patient-centered functional endpoint, but there was no independent repeated trial of the same regimen, giving D with 34 points.
Counterpoint. D does not mean all rehabilitation is harmful; it is specific to AVERT's frequent, higher-dose protocol within 24 hours.
Rejudgment record. Cross-check applied — We cross-checked the AVERT paper, registry, and public report for centralized randomization, masked assessment, ITT denominators, the prespecified mRS endpoint, events, and public funding.
| Endpoint | P | Symptom or function itself is the target - including patient reports and performance tests |
| Replication | R1 | Single confirmatory trial |
| Independence | I2 | Decisive evidence is publicly or non-profit funded |
| Effect size | E- | Harm increased in the trials |
| Precision | C0 | The confidence interval leaves room for benefit |
Stored derived and displayed grades match; this is not a current recalculation or validity check (D).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Increased favorable functional recovery at three months | D | Adjusted OR was 0.73, significantly in the opposite direction. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| AVERT Trial Collaboration group, 2015 AVERT | Assessor-masked multinational randomized trial at 56 stroke units | 2,104 randomized (1,054/1,050); 2,083 at three months (1,038/1,045) | NHMRC, Singapore Health, NIHR, and UK stroke charities | Favorable three-month functional outcome, mRS 0 to 2 | 480/1,038 (46.2%) versus 525/1,045 (50.2%), adjusted OR 0.73 (95% CI 0.59 to 0.90), P=0.004 | Pivotal independent large functional-outcome RCT |
Receipt — 1 References
All 1 cited sources were verified for existence at the original page (as of 2026-08-14).
Final verification and publication gate: Codex · Evidence date: 2026-08-14 · Corrections: none
Cite this verdict
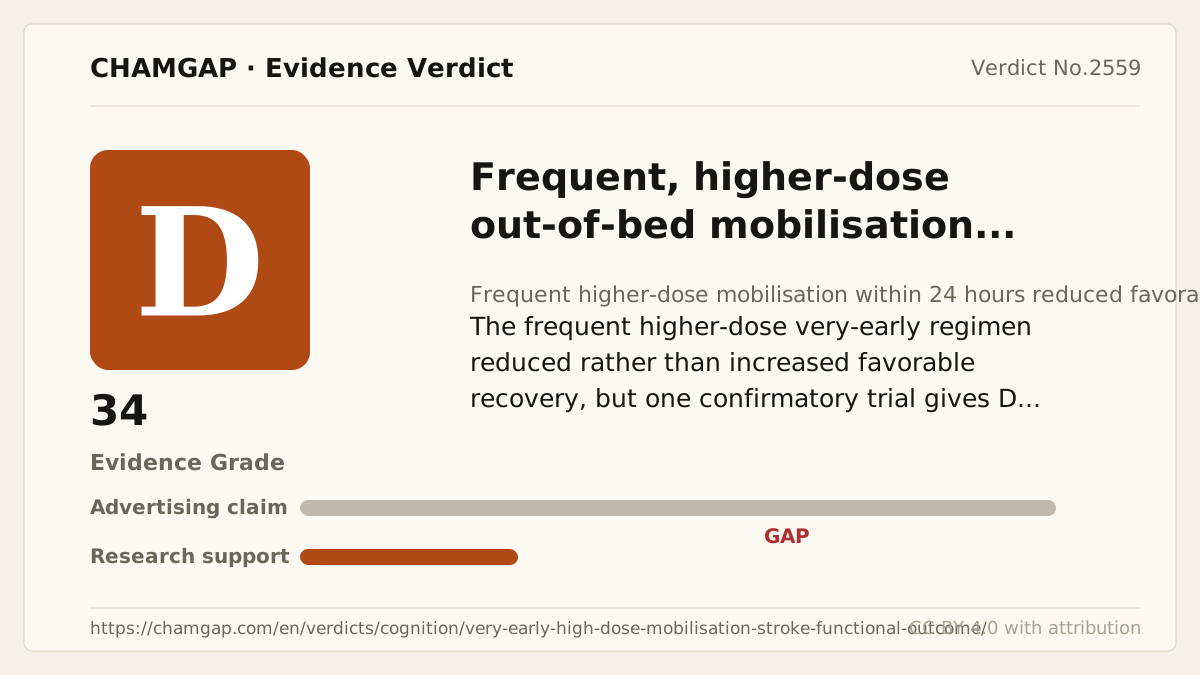
[Chamgap] Frequent higher-dose mobilisation within 24 hours after stroke x better functional recovery — Evidence Grade D·34. 1 cited sources checked. Source: https://chamgap.com/en/verdicts/cognition/very-early-high-dose-mobilisation-stroke-functional-outcome/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.