
MRI-selected alteplase,
does it really help with Increased functional independence at 90 days after acute ischemic stroke of unknown onset?
research showsThe grade is B. WAKE-UP randomized 503 patients with an acute DWI lesion but no corresponding FLAIR hyperintensity. Observed 90-day mRS 0-1 occurred in 131/246 (53.3%) with alteplase versus 102/244 (41.8%) with placebo, an 11.5-point absolute difference; adjusted OR 1.61 (95% CI 1.09-2.36). It remains one confirmatory trial stopped at 503 rather than 800 because EU funding was ending, giving B with 70 points.
ads claimThe result does not mean every stroke noticed on awakening should receive thrombolysis. It applies after specialist confirmation of no hemorrhage, a DWI lesion without corresponding FLAIR hyperintensity, thrombolysis eligibility, and the thrombectomy pathway.
Useful facts when choosing a product
- Alteplase was dosed at 0.9 mg/kg, with 10% as a bolus and the remainder infused over 60 minutes.
- MRI was both an eligibility tool and an assessment tool; company supply was not reported.
- WAKE-UP is an MRI-selected stroke thrombolysis trial, not the PRAMI myocardial-infarction PCI trial.
Chamgap Semantic Classification Code
Candidate index · review held
UNK.alteplase-selected-by-mri-dwi-flair-mismatch.intravenous.functional-independence-at-after-acute-ischemic-stroke-of-unknown-onset.increase.placeboUnknown > alteplase selected by MRI DWI-FLAIR mismatch > Intravenous > functional independence at after acute ischemic stroke of unknown onset > Increase claim > Placebo
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
Sixty-one centers in eight European countries assigned 254 and 249 patients through a web-based permuted-block procedure and used matching placebo under double masking. The primary efficacy population was, in the article's words, ‘the intention-to-treat population, which included all the patients who had undergone randomization,’ all 503 patients. Outcomes were observed in 490, 246 versus 244, but ‘Missing data in the primary outcome analysis were imputed with the use of multiple imputation techniques,’ so 13 were not discarded. Enrollment stopped at 503 of a planned 800 because EU funding was expected to cease, ‘without an interim analysis of trial data.’ This was early stopping for resource limitations, not a prespecified efficacy or harm boundary and not termination after an unplanned interim analysis. EU FP7 grant 278276 funded the trial, and the article states, ‘There was no industry funding or involvement in any aspect of the trial.’ Author company relationships were disclosed, but company supply of alteplase, placebo, or MRI assessment tools was not reported.
Why this is classified as B (70)
A publicly funded double-blind placebo-controlled trial found a large functional benefit, but lack of independent replication and early stopping when funding ended give B with 70 points.
Counterpoint. B does not mean the observed benefit was small. It reflects uncertainty from one early-stopped trial and imprecise harm estimates.
Rejudgment record. Cross-check applied — Cross-checked WAKE-UP's 503-person intention-to-treat analysis, multiple imputation, MRI-selected functional endpoint, public funding, and resource-driven early stopping
| Endpoint | P | Symptom or function itself is the target - including patient reports and performance tests |
| Replication | R1 | Single confirmatory trial |
| Independence | I2 | Decisive evidence is publicly or non-profit funded |
| Effect size | E+ | Meets the clinically important threshold |
Stored derived and displayed grades match; this is not a current recalculation or validity check (B).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Increased functional independence at 90 days | B | The observed absolute difference was 11.5 points and the adjusted intention-to-treat OR was 1.61. |
| Applicability to every stroke of unknown onset | ? | The trial required a specific DWI-FLAIR mismatch and thrombolysis eligibility. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| Thomalla G et al. 2018 WAKE-UP | Multicenter double-blind placebo-controlled superiority randomized trial | 503 randomized and in intention-to-treat, 254/249; 490 observed at 90 days, 246/244, with 13 multiply imputed | EU Seventh Framework Programme grant 278276; no industry funding or involvement | mRS 0-1 at 90 days | Observed 53.3% versus 41.8%, absolute difference +11.5 points; adjusted OR 1.61 (95% CI 1.09-2.36), P=.02 | Single publicly funded confirmatory trial stopped early for resource limitations |
Receipt — 1 References
All 1 cited sources were verified for existence at the original page (as of 2026-08-18).
Final verification and publication gate: Codex · Evidence date: 2026-08-18 · Corrections: none
Cite this verdict
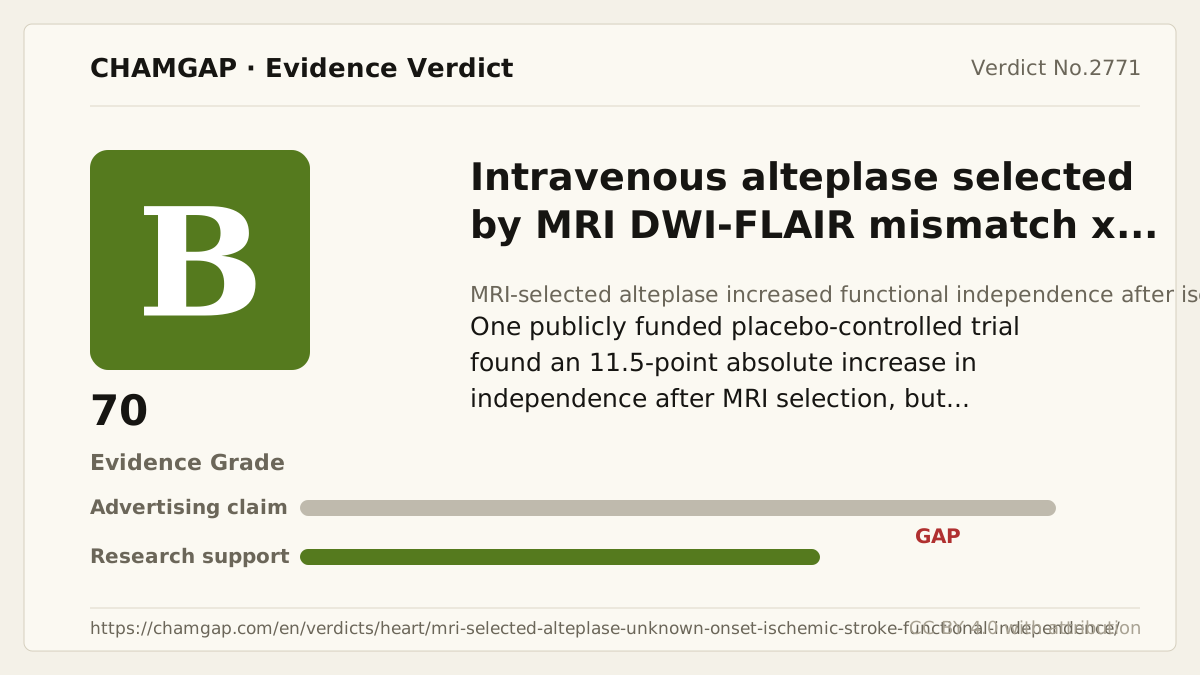
[Chamgap] MRI-selected alteplase x functional independence after stroke of unknown onset — Evidence Grade B·70. 1 cited sources checked. Source: https://chamgap.com/en/verdicts/heart/mri-selected-alteplase-unknown-onset-ischemic-stroke-functional-independence/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.