
LUCAS mechanical chest compression,
does it really help with Increased survival and survival with favorable neurologic outcome versus standard manual compression?
research showsThe grade is D. In 2,589-participant LINC, four-hour survival was 307/1,300 (23.6%) versus 305/1,289 (23.7%), difference -0.05 points (95% CI -3.3 to 3.2). On the common roughly 30-day timescale, one-month survival was 112/1,300 (8.6%) versus 109/1,289 (8.5%), difference 0.16 points (95% CI -2.0 to 2.3), and favorable neurologic survival was 105/1,300 (8.1%) versus 94/1,289 (7.3%). In 4,471-participant PARAMEDIC, 30-day survival was 104/1,652 (6.3%) versus 193/2,819 (6.8%), adjusted OR 0.86 (95% CI 0.64 to 1.15). Two large trials repeatedly failed to support increased survival, but no prespecified clinical-benefit threshold allows exclusion of meaningful benefit, giving D with 34 points.
ads claimThe device's ability to repeat compressions at set parameters is real, but that fact does not establish greater patient survival than standard manual CPR. Operational advantages in special transport or procedural settings require a separate claim.
Useful facts when choosing a product
- LUCAS is a piston device that repeats programmed chest compressions and can replace continuous manual compression by rescuers.
- LINC compared a mechanical-CPR algorithm that also included defibrillation during ongoing compressions.
- In PARAMEDIC, 60% of the mechanical-assigned group received the device, versus less than 1% of controls.
Chamgap Semantic Classification Code
Candidate index · review held
UNK.lucas-automated-mechanical-chest-compression.UNK.survival-and-survival-with-favorable-neurologic-outcome.increase.UNKUnknown > LUCAS automated mechanical chest compression > Unknown > survival and survival with favorable neurologic outcome > Increase claim > Unknown
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
Rubertsson's LINC individually randomized 2,589 participants and used the NCT00609778 four-hour survival outcome as primary. It was initiated by Uppsala University and sponsored by Physio-Control/Jolife. Perkins's PARAMEDIC cluster-randomized ambulance vehicles and analyzed 4,471 patients, using 30-day survival from ISRCTN08233942 as primary. Outcome collection was masked, but only 985/1,652 (60%) assigned to mechanical compression actually received LUCAS, an implementation limitation. PARAMEDIC was NIHR funded.
Why this is classified as D (34)
Independent large trials repeatedly failed to support increased survival in the same indication, but no prespecified clinical-benefit threshold and benefit-compatible intervals prevent a definitive F, giving D with 34 points.
Counterpoint. D does not mean the device has no operational role. It means superiority over manual CPR for survival has not been established.
Rejudgment record. Cross-check applied — We cross-checked primary and common longer-term survival, neurologic survival, confidence intervals, funding, randomization units, and actual device use against both articles and registries and confirmed the absence of a prespecified clinical-benefit threshold.
| Endpoint | H | Hard endpoint - actual events such as death |
| Replication | RX | Repeatedly refuted in the same indication |
| Independence | I1 | Mixed funding sources |
| Effect size | E0 | Null |
| Precision | C0 | The confidence interval leaves room for benefit |
Stored derived and displayed grades match; this is not a current recalculation or validity check (D).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| LUCAS improves survival over manual CPR after out-of-hospital cardiac arrest. | D | Two large trials found no benefit in four-hour, 30-day, or common longer-term survival outcomes. |
| LUCAS improves survival with favorable neurologic outcome over manual CPR after out-of-hospital cardiac arrest. | D | Neither LINC at one month nor PARAMEDIC at three months showed significant benefit. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| Rubertsson S et al., LINC 2014 | Individually randomized trial across six emergency medical systems | 2,589 randomized and analyzed, 1,300 versus 1,289 | Uppsala University institutional grants and Physio-Control/Jolife AB sponsorship | Primary four-hour survival; one- and six-month survival with favorable neurologic status | Four-hour survival 307/1,300 versus 305/1,289, difference -0.05 points (95% CI -3.3 to 3.2); one-month survival 112 versus 109, difference 0.16 (-2.0 to 2.3); one-month favorable neurologic survival 105 versus 94, difference 0.78 (-1.3 to 2.8) | Large mixed-funded repeatedly null evidence |
| Perkins GD et al., PARAMEDIC 2015 | Pragmatic cluster-randomized trial at the ambulance-vehicle level | 4,471 in intention-to-treat analysis, 1,652 versus 2,819; 985 mechanical-assigned patients received the device | NIHR Health Technology Assessment Programme | Thirty-day survival and three-month survival with favorable neurologic outcome | Thirty-day survival 104/1,652 versus 193/2,819, adjusted OR 0.86 (95% CI 0.64 to 1.15); favorable neurologic survival at three months 77/1,649 versus 168/2,815 | Large independent publicly funded repeatedly null evidence |
Receipt — 2 References
All 2 cited sources were verified for existence at the original page (as of 2026-08-14).
Final verification and publication gate: Codex · Evidence date: 2026-08-14 · Corrections: none
Cite this verdict
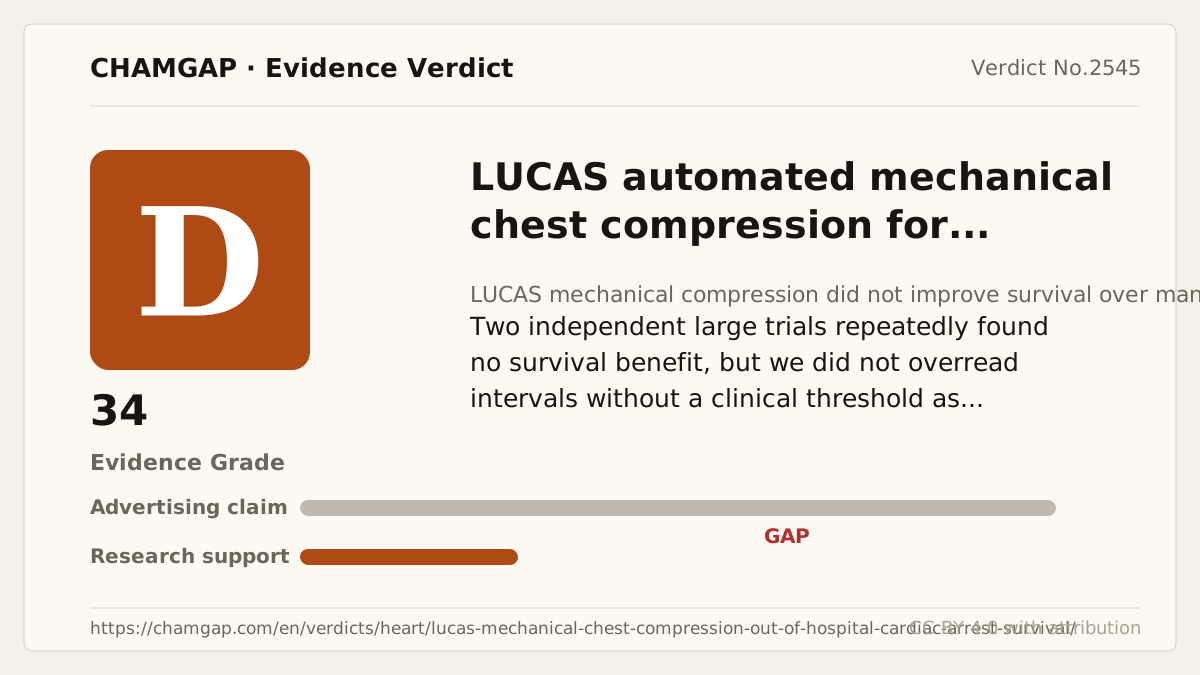
[Chamgap] LUCAS mechanical chest compression x survival after out-of-hospital cardiac arrest — Evidence Grade D·34. 2 cited sources checked. Source: https://chamgap.com/en/verdicts/heart/lucas-mechanical-chest-compression-out-of-hospital-cardiac-arrest-survival/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.