
Liberal transfusion in acute MI with anemia,
does it really help with Reduction in 30-day death or recurrent myocardial infarction versus restrictive transfusion in acute MI with anemia?
research showsThe grade is D. MINT found death or recurrent MI in 295/1,749 (16.9%) with restriction versus 255/1,755 (14.5%) with liberal transfusion, restrictive-versus-liberal RR 1.15, 95% CI 0.99 to 1.34, P=0.07. The 2.4-point numerical difference favored liberal transfusion, but the primary test was borderline and not significant.
ads claimP=0.07 cannot be rounded into a significant reduction, but the interval also does not establish no benefit.
Useful facts when choosing a product
- MINT used a 10-g/dL liberal threshold and a 7-to-8-g/dL restrictive strategy.
- Mean transfusion was 2.5 versus 0.7 red-cell units.
- Recurrent MI was adjudicated by a treatment-blinded committee.
Chamgap Semantic Classification Code
Candidate index · review held
UNK.liberal-red-cell-transfusion-strategy.UNK.death-or-recurrent-myocardial-infarction.reduce.UNKUnknown > Liberal red-cell transfusion strategy > Unknown > death or recurrent myocardial infarction > Reduction claim > Unknown
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
MINT analyzed 3,504 patients at 126 sites. Death was 173/1,749 (9.9%) versus 146/1,755 (8.3%), and recurrent MI was 8.5% versus 7.2%. NHLBI and other public sources funded the trial. REALITY randomized 668 and found its broader 30-day composite in 36 (11.0%) versus 45 (14.0%), RR 0.79 with a two-sided 95% upper bound of 1.19 inside its 1.25 noninferiority margin. Because REALITY tested restrictive noninferiority with a different composite, it was not counted as replication of MINT's liberal-superiority primary question.
Why this is classified as D (34)
The primary hard endpoint in a large publicly funded trial was null and imprecise enough to retain benefit, giving D with 34 points.
Counterpoint. The point estimate and several components favor liberal transfusion, so clinical equivalence is not established.
Rejudgment record. Cross-check applied — MINT primary outcome, thresholds, actual transfusion units, blinded adjudication, and comparison with REALITY
| Endpoint | H | Hard endpoint - actual events such as death |
| Replication | R1 | Single confirmatory trial |
| Independence | I2 | Decisive evidence is publicly or non-profit funded |
| Effect size | E0 | Null |
| Precision | C0 | The confidence interval leaves room for benefit |
Stored derived and displayed grades match; this is not a current recalculation or validity check (D).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Reduced 30-day death or recurrent MI | D | The primary endpoint was null at P=0.07. |
| Increased red-cell use | B | Mean use clearly separated, 2.5 versus 0.7 units. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| Carson JL et al. 2023 MINT | Open-label multicenter superiority trial with blinded recurrent-MI adjudication | 3,504 in primary analysis, 1,749 versus 1,755 | US NHLBI and other public funding | All-cause death or recurrent MI through 30 days | 295/1,749 (16.9%) versus 255/1,755 (14.5%), restrictive-versus-liberal RR 1.15, 95% CI 0.99 to 1.34, P=0.07 | Decisive large trial |
| Ducrocq G et al. 2021 REALITY | Open-label noninferiority trial | 668 randomized; 646 in the 30-day as-treated analysis | Public grants from the French Ministry of Health and Spanish Ministry of Economy and Competitiveness | 30-day composite of death, stroke, recurrent MI, or emergency revascularization | Restrictive 36 (11.0%) versus liberal 45 (14.0%), RR 0.79, upper 95% bound 1.19 within the 1.25 margin | Supportive trial addressing a different composite and directional question |
Receipt — 2 References
All 2 cited sources were verified for existence at the original page (as of 2026-08-06).
Final verification and publication gate: Codex · Evidence date: 2026-08-06 · Corrections: none
Cite this verdict
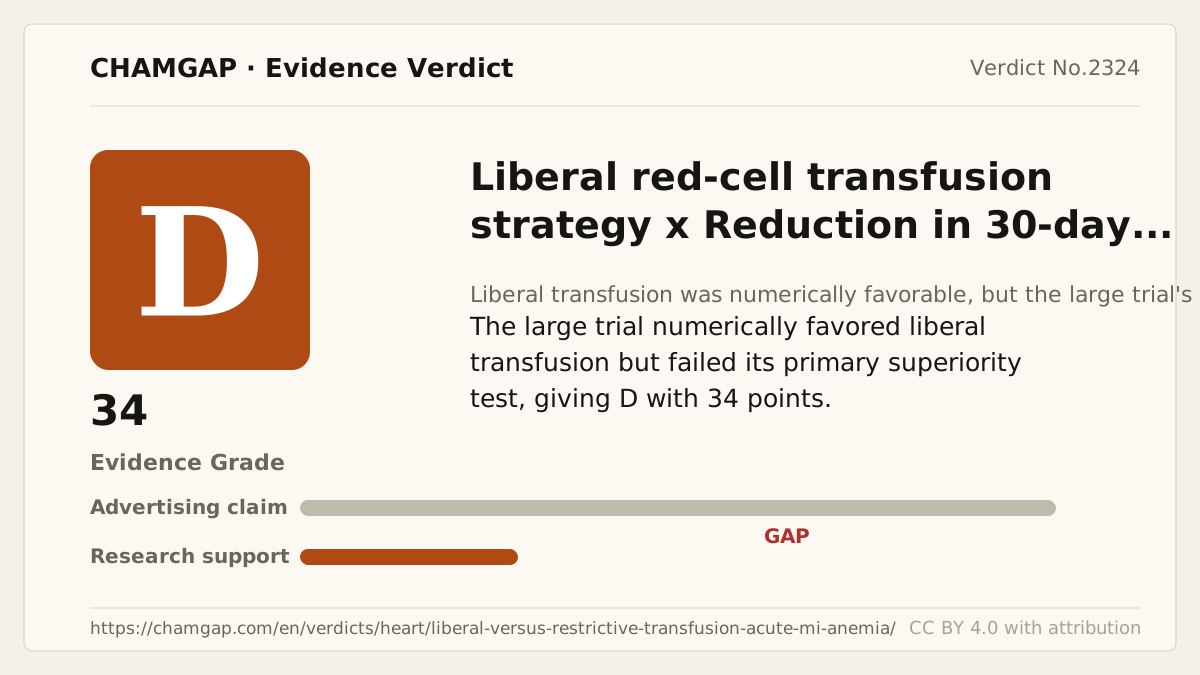
[Chamgap] Liberal transfusion in acute MI with anemia x death or reinfarction — Evidence Grade D·34. 2 cited sources checked. Source: https://chamgap.com/en/verdicts/heart/liberal-versus-restrictive-transfusion-acute-mi-anemia/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.