
Hydroxyurea and phlebotomy switch,
does it really help with Maintained secondary stroke prevention while reducing iron overload in children with sickle cell anemia?
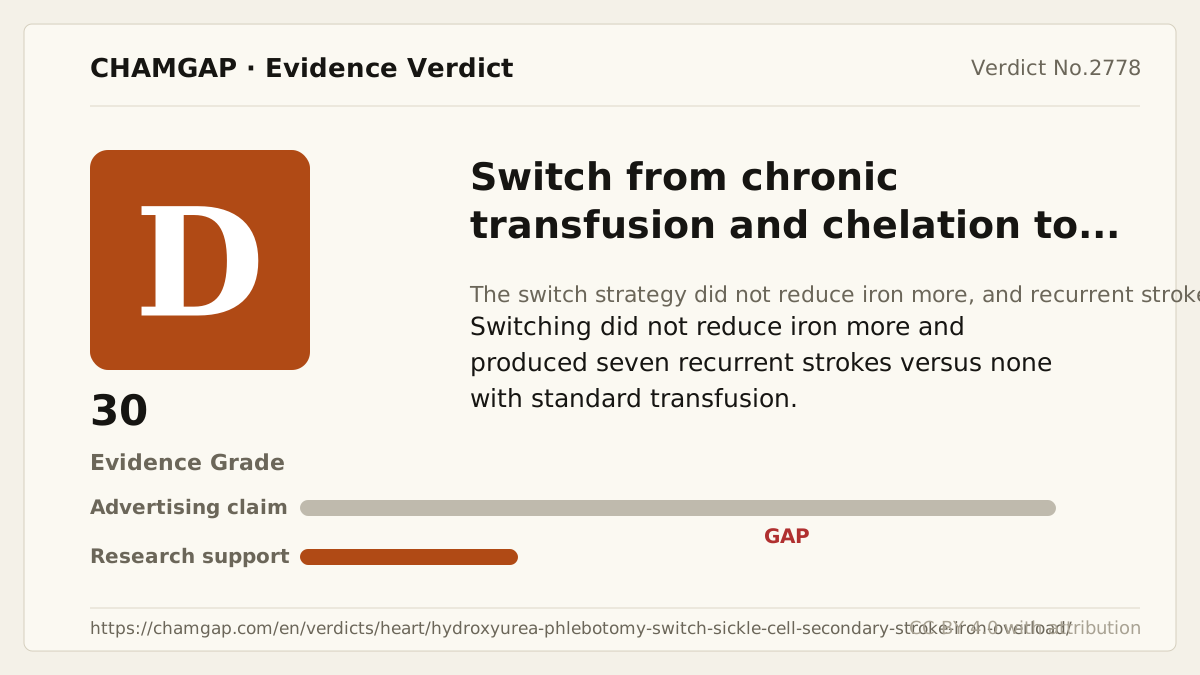
research showsThe grade is D. In SWiTCH, recurrent stroke occurred in 0/66 with standard transfusion and chelation versus 7/67, 10%, after switching, P<.05. Liver iron was 16.6 versus 15.7 mg/g and was not superior with switching. The trial stopped for futility of the composite strategy. NHLBI provided public funding, but Novartis supplied deferasirox used as a treatment material in the standard arm, making funding mixed. One early-stopped harmful trial gives D with 30 points.
ads claimIt is not valid to claim that patients can stop transfusions while preserving stroke prevention and reducing iron. Iron superiority failed, seven strokes occurred only after switching, and one was fatal hemorrhagic stroke.
Useful facts when choosing a product
- The switch arm overlapped transfusion for four to nine months during hydroxyurea escalation before phlebotomy began.
- Novartis-supplied deferasirox was a treatment material in the standard arm, not an assessment tool.
- This question concerns switching secondary stroke prevention, not general treatment of sickle cell complications.
Chamgap Semantic Classification Code
Candidate index · review held
M.switch-from-chronic-transfusion-and-chelation-to-hydroxyurea-and-phlebotomy.intravenous.maintained-secondary-stroke-prevention-while-reducing-iron-overload-with-sickle-cell-anemia.prevent.MULTIMedicinal interventions > Switch from chronic transfusion and chelation to hydroxyurea and phlebotomy > Intravenous > Maintained secondary stroke prevention while reducing iron overload with sickle cell anemia > Occurrence-prevention claim > Multiple: primary unresolved
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
At 26 US centers, 133 children were assigned to transfusion plus chelation, 66, or hydroxyurea plus phlebotomy, 67, and evaluated by intention to treat. Treatment was open, but neurological events underwent central formal adjudication. At the first scheduled interim analysis, liver iron was similar, 16.6 versus 15.7 mg/g dry weight, making composite success futile; the DSMB recommended closure and NHLBI stopped the trial. This was prespecified interim composite-endpoint futility, not resource limitation, a prespecified efficacy boundary, a prespecified harm boundary, or an unplanned interim look. NHLBI U01 grants funded the trial, while Novartis donated deferasirox actually used in the standard treatment arm. No supply of hydroxyurea or assessment tools was reported. Avoidable limitations were noninferiority design, a total sample below 200, early stopping, and active control without placebo.
Why this is classified as D (30)
Failed liver-iron superiority plus significantly more recurrent stroke in one early-stopped trial gives D with 30 points.
Counterpoint. D does not label hydroxyurea harmful for every sickle cell indication. It applies to replacing transfusion in children with prior stroke and iron overload.
Rejudgment record. Cross-check applied — Accounts for the composite noninferiority-superiority threshold, 133-person ITT population, prespecified futility stopping, significant stroke increase, and Novartis treatment-material supply
| Endpoint | H | Hard endpoint - actual events such as death |
| Replication | R1 | Single confirmatory trial |
| Independence | I1 | Mixed funding sources |
| Effect size | E- | Harm increased in the trials |
| Precision | C0 | The confidence interval leaves room for benefit |
Stored derived and displayed grades match; this is not a current recalculation or validity check (D).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Maintained secondary stroke prevention | D | There were zero versus seven strokes, a significant adverse result. |
| Superior reduction of iron overload | D | Liver iron was 16.6 versus 15.7 mg/g and was not superior. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| Ware RE, Helms RW et al. 2012 SWiTCH | Open-label, centrally adjudicated randomized phase 3 trial with a two-component noninferiority/superiority hypothesis | 133 randomized and analyzed by intention to treat, 66 standard and 67 switch | Public NHLBI grants; Novartis donated deferasirox used as standard-arm trial treatment | Joint achievement of recurrent-stroke noninferiority and liver-iron superiority over 30 months | Stroke 0/66 versus 7/67, P<.05; liver iron 16.6 versus 15.7 mg/g without switch-arm superiority; stopped at prespecified interim futility analysis | Clinical harm and failed composite primary strategy |
Receipt — 1 References
All 1 cited sources were verified for existence at the original page (as of 2026-08-18).
Final verification and publication gate: Codex · Evidence date: 2026-08-18 · Corrections: none
Cite this verdict
[Chamgap] Hydroxyurea and phlebotomy switch x secondary stroke and iron overload in sickle cell anemia — Evidence Grade D·30. 1 cited sources checked. Source: https://chamgap.com/en/verdicts/heart/hydroxyurea-phlebotomy-switch-sickle-cell-secondary-stroke-iron-overload/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.