
Aggressive fluid resuscitation,
does it really help with Improved clinical outcomes and fluid overload?
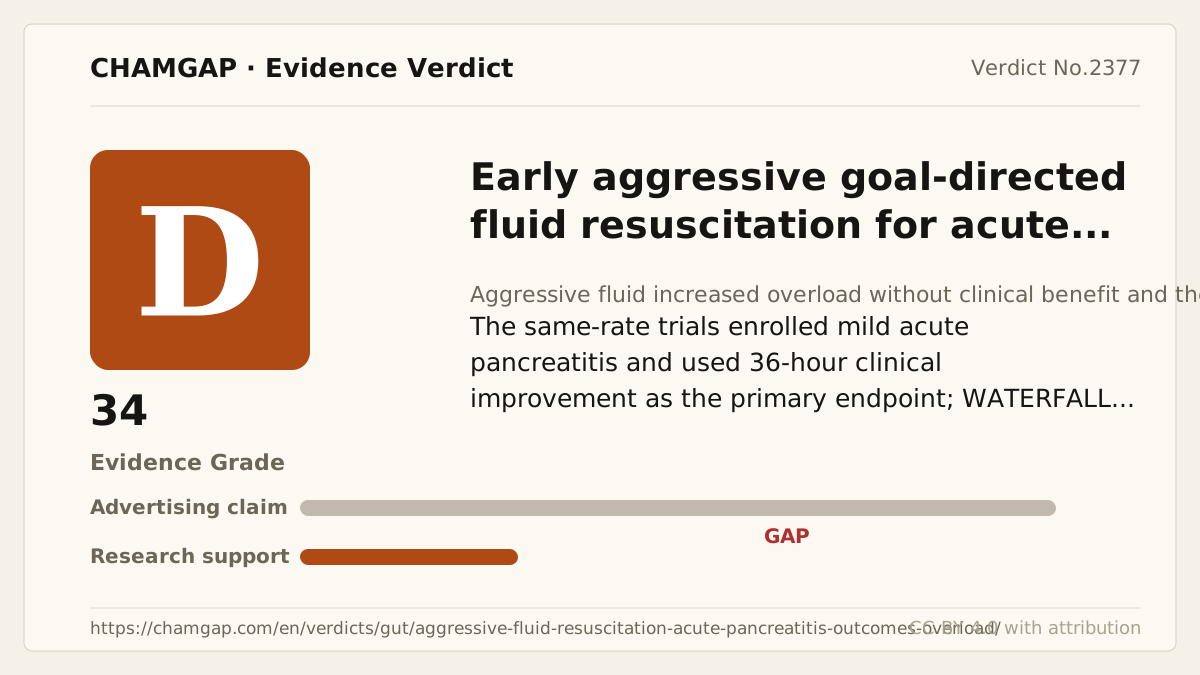
research showsThe grade is D with 34 points. WATERFALL found no reduction in moderately severe or severe pancreatitis and increased fluid overload from 8/127 (6.3%) to 25/122 (20.5%). Buxbaum 2017, Angsubhakorn 2021, and Cuéllar-Monterrubio 2020 used substantially the same 3 versus 1.5 mL/kg/h regimens, but different populations and endpoints mean they did not repeat the same comparison, so this is not F.
ads claimMore fluid did not mean faster recovery. Although small trials used the same rates, their mild population and 36-hour clinical-improvement endpoint did not repeat WATERFALL's question about moderately severe or severe pancreatitis and fluid overload.
Useful facts when choosing a product
- The aggressive regimen used a 20 mL/kg bolus then 3 mL/kg/h; the moderate regimen used a bolus only for hypovolemia then 1.5 mL/kg/h.
- The list of prespecified safety endpoints contained only fluid overload; the result was 25/122 versus 8/127, adjusted RR 2.85 (95% CI 1.36 to 5.94; p=0.004).
- Buxbaum 2017 (60 participants), Angsubhakorn 2021 (44), and Cuéllar-Monterrubio 2020 used substantially the same rates but studied mild disease and 36-hour clinical improvement. Their result direction was not checked.
- An O'Brien–Fleming group-sequential boundary was applied to the interim analysis of the primary efficacy outcome. No separate adjustment covering the main safety endpoint and all secondary endpoints was specified.
Chamgap Semantic Classification Code
Candidate index · review held
UNK.early-aggressive-goal-directed-fluid-resuscitation.UNK.clinical-outcomes-and-fluid-overload.improve.UNKUnknown > Early aggressive goal-directed fluid resuscitation > Unknown > clinical outcomes and fluid overload > Improvement claim > Unknown
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
de-Madaria et al. randomized 249 patients at 18 centers, 122 to aggressive and 127 to moderate resuscitation. Aggressive care used a 20 mL/kg bolus then 3 mL/kg/h; moderate care used a 10 mL/kg bolus only for hypovolemia then 1.5 mL/kg/h. Moderately severe or severe pancreatitis occurred in 22.1% versus 17.3%, adjusted RR 1.30 (95% CI 0.78 to 2.18; P=0.32). The only named prespecified safety endpoint was fluid overload: 25/122 (20.5%) versus 8/127 (6.3%), adjusted RR 2.85 (95% CI 1.36 to 5.94; p=0.004). An O'Brien–Fleming group-sequential boundary was applied to the interim analysis of the primary efficacy outcome. No separate adjustment covering the main safety endpoint and all secondary endpoints was specified. The monitoring board stopped the trial because excess harm was not balanced by a benefit trend.
Why this is classified as D (34)
A publicly funded RCT found no benefit and significant harm. The other same-rate trials addressed different populations and endpoints rather than repeating the same question, giving D with 34 points.
Counterpoint. D rejects claimed benefit from aggressive dosing; it does not mean withholding all fluid in acute pancreatitis.
Rejudgment record. Cross-check applied — Three trials used the same 3 versus 1.5 mL/kg/h rates but studied mild disease and 36-hour clinical improvement, not WATERFALL's moderately severe or severe pancreatitis and fluid-overload question
| Endpoint | H | Hard endpoint - actual events such as death |
| Replication | R1 | Single confirmatory trial |
| Independence | I2 | Decisive evidence is publicly or non-profit funded |
| Effect size | E- | Harm increased in the trials |
| Precision | C0 | The confidence interval leaves room for benefit |
Stored derived and displayed grades match; this is not a current recalculation or validity check (D).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Reduced moderately severe or severe pancreatitis | D | No benefit was found, 22.1% versus 17.3%. |
| Increased fluid overload | B | It increased significantly, 25/122 versus 8/127, in one trial. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| de-Madaria E et al. 2022 WATERFALL | Open-label 18-center randomized goal-directed fluid trial stopped early | 249 randomized and analyzed, 122 versus 127 | Public and nonprofit support from Instituto de Salud Carlos III, the Spanish Association of Gastroenterology, and ISABIAL | Moderately severe or severe pancreatitis in hospital; main safety outcome fluid overload | Primary outcome 22.1% versus 17.3%, RR 1.30, 95% CI 0.78 to 2.18; fluid overload 25/122 versus 8/127, RR 2.85, 95% CI 1.36 to 5.94 | Pivotal single randomized trial |
Receipt — 2 References
All 2 cited sources were verified for existence at the original page (as of 2026-08-07).
Final verification and publication gate: Codex · Evidence date: 2026-08-07 · Corrections: none
Cite this verdict
[Chamgap] Aggressive fluid resuscitation x clinical outcomes and fluid overload in acute pancreatitis — Evidence Grade D·34. 2 cited sources checked. Source: https://chamgap.com/en/verdicts/gut/aggressive-fluid-resuscitation-acute-pancreatitis-outcomes-overload/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.