
Two units of prehospital thawed plasma,
does it really help with Reduced 28- to 30-day mortality versus crystalloid-centered standard resuscitation?
research showsThe grade is B. In 501 air-transport patients, PAMPer found 30-day mortality of 23.2% versus 33.0%, difference -9.8 points (95% CI -18.6 to -1.0). In contrast, COMBAT's 125-person urban ground-transport analysis found 28-day mortality of 10/65 (15%) versus 6/60 (10%), effect estimate 1.54 (95% CI 0.60 to 3.98), P=.37. However, COMBAT's broad interval includes PAMPer's relative-risk estimate of about 0.70, and median transport differed at roughly 16 to 19 versus 40 to 42 minutes. The null study is imprecise and context differs, so it does not establish statistical conflict; two human trials exist, making this B with 76 points rather than unknown.
ads claimTwo units of thawed plasma can be delivered before hospital arrival, and survival improved during longer air transport. Advertising benefit across rapid urban transfers without transport context would exceed the trials.
Useful facts when choosing a product
- PAMPer and COMBAT both tested two units of prehospital plasma but differed in transport mode and time.
- Existing plasma verdicts in the corpus concern albumin, platelet-rich plasma, or young-donor plasma; this verdict concerns thawed plasma during trauma transport.
- Hunter B Moore, listed as Moore HB, is COMBAT's first author; Ernest E Moore is second.
Chamgap Semantic Classification Code
Candidate index · review held
UNK.two-units-of-thawed-plasma-before-hospital-arrival.UNK.28-to-mortality.reduce.UNKUnknown > Two units of thawed plasma before hospital arrival > Unknown > 28- to mortality > Reduction claim > Unknown
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
Sperry JL, Guyette FX, Brown JB, Yazer MH and colleagues conducted the multicenter cluster-randomized PAMPer trial with U.S. Army Medical Research and Materiel Command funding. COMBAT's first author was Moore HB; Moore EE was second author. COMBAT randomized 144 but used 125 in its main analysis after postrandomization exclusions, was small, and stopped for futility. Both trials used U.S. Department of Defense-family public funding, so different investigators did not establish replication from a separate funding source.
Why this is classified as B (76)
PAMPer provided publicly funded hard-outcome benefit. COMBAT was imprecise, included the PAMPer effect estimate, and differed in transport time, so it was neither exact replication nor true conflict; one direct confirmatory trial gives B with 76 points.
Counterpoint. B does not establish benefit during every transport duration; benefit may be concentrated when definitive blood access is delayed.
Rejudgment record. Cross-check applied — We cross-checked mortality denominators and intervals, transport times, analysis populations, funding, and whether COMBAT excluded the PAMPer effect across both trials.
| Endpoint | H | Hard endpoint - actual events such as death |
| Replication | R1 | Single confirmatory trial |
| Independence | I2 | Decisive evidence is publicly or non-profit funded |
| Effect size | E+ | Meets the clinically important threshold |
Stored derived and displayed grades match; this is not a current recalculation or validity check (B).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Reduced 30-day mortality during longer air transport | B | PAMPer found an absolute difference of -9.8 points. |
| Reduced 28-day mortality during rapid urban ground transport | D | COMBAT found 15% versus 10%, P=.37, without benefit but did not exclude the PAMPer effect. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| Sperry JL, Guyette FX, Brown JB, Yazer MH et al. 2018 PAMPer | Multicenter cluster-randomized air-medical transport trial | 501 participants, 230 versus 271 | U.S. Army Medical Research and Materiel Command | 30-day mortality | 23.2% versus 33.0%, difference -9.8 points (95% CI -18.6 to -1.0), P=.03 | Survival benefit during longer air transport |
| Moore HB, Moore EE, Chapman MP et al. 2018 COMBAT | Single-center randomized urban ground-transport trial | 144 randomized and 125 in the main analysis, 65 versus 60 | U.S. Department of Defense and NIH support | 28-day mortality | 10/65 (15%) versus 6/60 (10%), effect estimate 1.54 (95% CI 0.60 to 3.98), P=.37 | Null result during rapid urban transport |
Receipt — 3 References
All 3 cited sources were verified for existence at the original page (as of 2026-08-14).
Final verification and publication gate: Codex · Evidence date: 2026-08-14 · Corrections: none
Cite this verdict
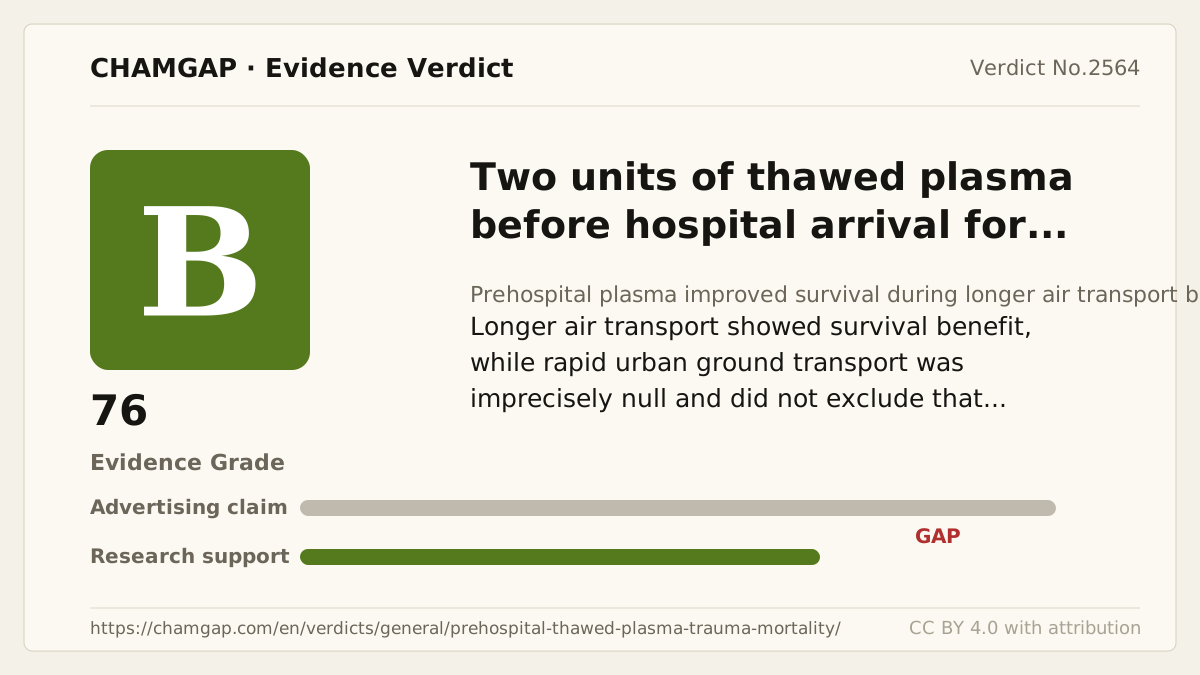
[Chamgap] Two units of prehospital thawed plasma x trauma mortality — Evidence Grade B·76. 3 cited sources checked. Source: https://chamgap.com/en/verdicts/general/prehospital-thawed-plasma-trauma-mortality/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.