
Early high-frequency oscillatory ventilation,
does it really help with Reduced short-term all-cause mortality versus contemporary lung-protective conventional ventilation?
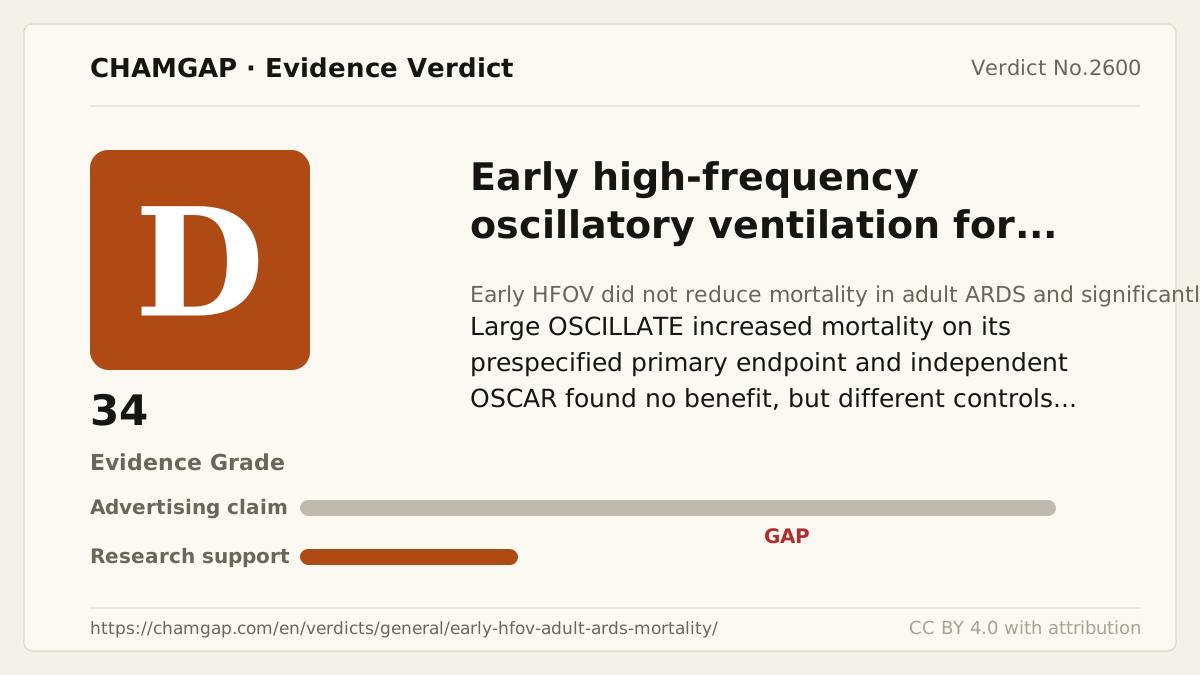
research showsThe grade is D with 34 points. In OSCILLATE, the prespecified primary outcome of in-hospital death occurred in 129/275 (46.9%) with HFOV versus 96/273 (35.2%) with lung-protective ventilation, RR 1.33 (95% CI 1.09 to 1.64), prompting termination for harm after 548 of 1,200 planned participants; guidelines also recommend against routine use. Independent OSCAR showed no 30-day benefit, 166/398 (41.7%) versus 163/397 (41.1%). Because the trials used materially different controls and devices, they were not counted as repetition of the same finding, so the grade is D rather than F.
ads claimHFOV truly delivers very small oscillating gas volumes at high frequency and can change physiologic measurements. That does not establish improved survival; more participants died in OSCILLATE.
Useful facts when choosing a product
- HFOV moves very small gas volumes at high frequency and may maintain a high mean airway pressure.
- OSCILLATE used more sedation, neuromuscular blockade, and vasoactive support in the HFOV group.
- CareFusion supplied nine ventilators and technical support to OSCILLATE but was reported not to participate in design, data, analysis, or manuscript preparation.
Chamgap Semantic Classification Code
Candidate index · review held
UNK.early-high-frequency-oscillatory-ventilation.UNK.short-term-all-cause-mortality.reduce.usual-careUnknown > Early high-frequency oscillatory ventilation > Unknown > short-term all-cause mortality > Reduction claim > Usual care
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
OSCILLATE randomized 548 adults across 39 ICUs, 275/273, with all-cause in-hospital mortality preregistered as primary. OSCAR randomized 795 across 29 UK ICUs, 398/397, with 30-day mortality as primary. OSCILLATE's day-28 RR of 1.41 and OSCAR's raw RR of about 1.02 are heterogeneous: the former showed harm and the latter was null. Moreover, OSCILLATE tested high-mean-airway-pressure HFOV against protocolized low-tidal-volume, high-PEEP ventilation, while OSCAR tested a Novalung R100 against each ICU's usual care; these cannot be counted as repetition of the same finding. Replication is therefore R1, not RX. Funding was independent—CIHR and King Abdullah sources versus UK NIHR—and the 2015 Lall HTA is a detailed OSCAR report, not a third trial.
Why this is classified as D (34)
Large OSCILLATE significantly increased prespecified primary mortality by 11.7 points, while independent OSCAR found no benefit. Because harm and null results from materially different controls and devices are not repetition of the same finding, replication is R1; E− plus strengths H, I2, and big_hard_rct gives D with 34 points.
Counterpoint. This applies to routine early HFOV in adult moderate-to-severe ARDS. Pediatric or neonatal use, rescue-only use, and different devices or protocols are separate questions.
Rejudgment record. Cross-check applied — Cross-checked primary endpoints, event counts, control and device differences, effect heterogeneity, early-stopping limitations, public funding, registrations, and duplicate OSCAR reporting against both NEJM articles and the OSCAR HTA
| Endpoint | H | Hard endpoint - actual events such as death |
| Replication | R1 | Single confirmatory trial |
| Independence | I2 | Decisive evidence is publicly or non-profit funded |
| Effect size | E- | Harm increased in the trials |
| Precision | C0 | The confidence interval leaves room for benefit |
Stored derived and displayed grades match; this is not a current recalculation or validity check (D).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Early HFOV reduces short-term mortality in moderate-to-severe adult ARDS | D | One independent trial increased mortality and another was null. |
| Early HFOV is safer than contemporary lung-protective ventilation | D | OSCILLATE increased in-hospital mortality by 11.7 percentage points. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| Ferguson ND et al.; OSCILLATE Trial Investigators; Canadian Critical Care Trials Group. 2013 OSCILLATE | Open-label multinational randomized trial in 39 ICUs, stopped early for harm | 548 randomized, 275 HFOV and 273 control, of 1,200 planned | Public and nonprofit support including Canadian Institutes of Health Research and King Abdullah International Medical Research Center; nine ventilators and technical support from CareFusion | Prespecified primary all-cause in-hospital mortality; day-28 mortality | In-hospital death 129/275 (46.9%) versus 96/273 (35.2%), RR 1.33 (1.09 to 1.64); day-28 death 111/275 (40.4%) versus 78/273 (28.6%), RR 1.41 (1.12 to 1.79) | Decisive trial showing harm on prespecified primary mortality |
| Young D et al.; OSCAR Study Group. 2013 OSCAR | Open-label randomized trial across 29 UK ICUs | 795 randomized, 398 HFOV and 397 control; 30-day vital status known for all | UK National Institute for Health Research Health Technology Assessment Programme 06/04/01 | Prespecified primary all-cause mortality at 30 days | 166/398 (41.7%) versus 163/397 (41.1%), absolute difference 0.6 points (95% CI -6.1 to 7.5); adjusted survival OR 1.03 (0.75 to 1.40) | Independent publicly funded repeated lack of benefit |
Receipt — 3 References
All 3 cited sources were verified for existence at the original page (as of 2026-08-14).
Final verification and publication gate: Codex · Evidence date: 2026-08-14 · Corrections: none
Cite this verdict
[Chamgap] Early high-frequency oscillatory ventilation x mortality in adult ARDS — Evidence Grade D·34. 3 cited sources checked. Source: https://chamgap.com/en/verdicts/general/early-hfov-adult-ards-mortality/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.