
Buttonhole fistula cannulation,
does it really help with Increased local infection, abscess, or bacteremia versus rope-ladder cannulation?
research showsThe grade is C. Buttonhole cannulation points toward increased infection: MacRae reported 50.0 versus 22.4 local-infection signs per 1,000 sessions, and Chow found 4/34 versus 1/35 in the same harm direction. The trials did not repeatedly refute the same question, and infection was not the pivotal trial's primary endpoint, so axis 6 B2 caps the result at C with 54 points.
ads claimIt is too strong to claim either proven safety or a precise multiple of infection risk. Communication should emphasize the safety signal and the need for asepsis, scab removal, and surveillance.
Useful facts when choosing a product
- Buttonhole repeatedly uses the same entry point, angle, and tract with blunt needles; rope ladder rotates sites.
- Pain, not infection, was MacRae's primary endpoint.
- No duplicate verdict using this intervention-outcome pair and pivotal PMIDs was identified.
Chamgap Semantic Classification Code
Candidate index · review held
UNK.buttonhole-cannulation-of-a-hemodialysis-arteriovenous-fistula.intravenous.local-infection-abscess-or-bacteremia.increase.UNKUnknown > Buttonhole cannulation of a hemodialysis arteriovenous fistula > Intravenous > local infection, abscess, or bacteremia > Increase claim > Unknown
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
MacRae randomized 140 participants. At eight weeks bacteremia was 1 versus 0 (P=1.00), while local infection signs were 50.0 versus 22.4 per 1,000 sessions (P=0.003). Over 12 months, two additional bacteremias and nine abscesses requiring intravenous antibiotics occurred with buttonhole versus none with standard needling (P=0.003). Chow analyzed 69 participants and found 4/34 versus 1/35 infections (P=0.11). Both trials had fewer than 200 participants and used open-label assessment of local infection signs; infection was secondary in MacRae.
Why this is classified as C (54)
Multiple small randomized trials support an increased-infection harm direction, making the effect E+. They do not constitute repeated refutation of the same question, so replication is R1, and the B2 limitation that infection was not the pivotal primary endpoint caps the result at C with 54 points.
Counterpoint. C does not mean the harm magnitude is precise. The direction favors concern, while pooled RR 3.34 (95% CI 0.91-12.20) still crosses no effect.
Rejudgment record. Cross-check applied — We coded the increased-infection direction as E+, kept replication at R1 because the trials did not repeatedly refute the same question, and applied the axis 6 B2 ceiling for a nonprimary infection outcome with open assessment.
| Endpoint | H | Hard endpoint - actual events such as death |
| Replication | R1 | Single confirmatory trial |
| Independence | I1 | Mixed funding sources |
| Effect size | E+ | Meets the clinically important threshold |
Stored derived and displayed grades match; this is not a current recalculation or validity check (C).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Buttonhole cannulation increases infection versus rope ladder. | C | Two trials point in the same harm direction, but axis 6 B2 imposes the ceiling. |
| Buttonhole definitively multiplies infection risk by a known amount. | D | Patient-level effects and the pooled interval are too imprecise to establish a multiplier. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| MacRae et al., CJASN 2012 | Centrally randomized open-label trial with 12-month extension | 140 randomized | Supported by the Kidney Foundation of Canada; no disclosures reported | Primary pain outcome; infection, hematoma, and bleeding tracked as prespecified complications | Local infection signs 50.0 versus 22.4/1,000 sessions (P=0.003); eight-week bacteremia 1 versus 0 (P=1.00); extension added two bacteremias and nine abscesses versus none (P=0.003) | Most direct trial, but infection was secondary |
| Chow et al., Journal of Renal Care 2011 | Multicenter prospective open-label randomized trial | 70 recruited; 69 in infection analysis (34/35) | Funding source not confirmed in publicly accessible material | Cannulation-site infection and other fistula complications | 4/34 (11.8%) versus 1/35 (2.9%), P=0.11; meta-analysis RR 4.53 (95% CI 0.48-42.82) | Related trial in the same harm direction but extremely imprecise |
Receipt — 3 References
Of 3 cited sources, 1 had limited original-page access (blocked or summary-only) and were verified via index/summary, marked partial; the rest were verified at the original page. As of 2026-08-14.
Final verification and publication gate: Codex · Evidence date: 2026-08-14 · Corrections: none
Cite this verdict
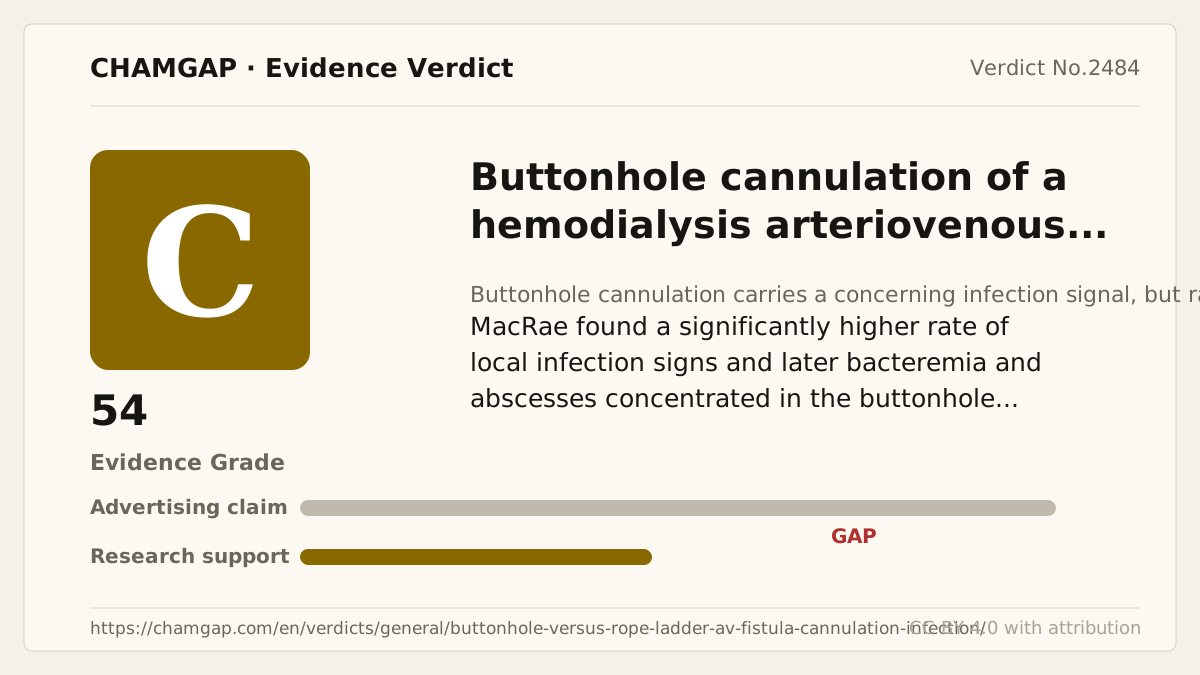
[Chamgap] Buttonhole fistula cannulation x increased infection — Evidence Grade C·54. 3 cited sources checked. Source: https://chamgap.com/en/verdicts/general/buttonhole-versus-rope-ladder-av-fistula-cannulation-infection/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.