
10-kHz spinal cord stimulation,
does it really help with At least 50% pain relief in refractory painful diabetic neuropathy?
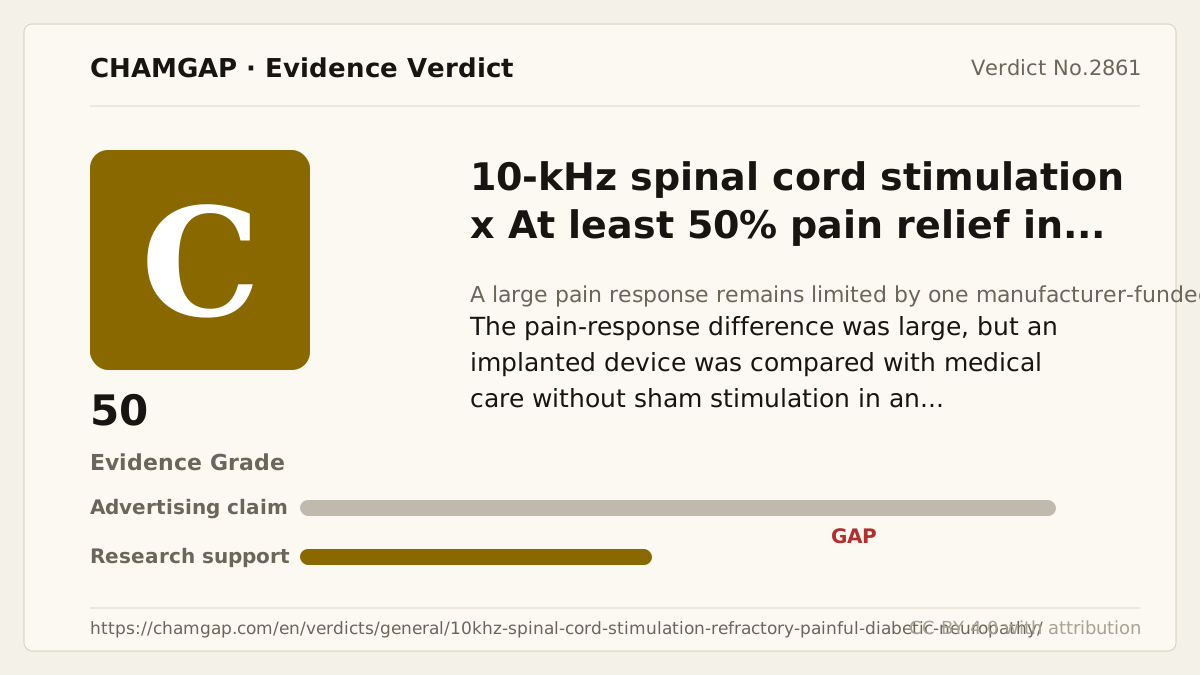
research showsThe grade is C. SENZA-PDN randomized 216 patients. In participants with known 3-month status, the primary composite occurred in 75/95 (79%) with 10-kHz SCS plus conventional medical management versus 5/94 (5%) with conventional management, an absolute difference of 73.6 points (95% CI 64.2 to 83.0). The study was open-label, pain was patient-reported, and Nevro funded the trial and participated in design, analysis, and manuscript work, so one manufacturer program gives C with 50 points.
ads claimSpinal stimulators are used in Korea under reimbursement and nonreimbursement pathways. A 2025 HIRA listing priced one rechargeable 16-contact IPG at KRW 13,265,100 before leads, trial stimulation, surgery, and hospitalization; actual patient cost depends on indication, materials, and coverage.
Useful facts when choosing a product
- Randomization assigned 103 to medical management and 113 to SCS plus management; the primary known-status analysis included 94 versus 95.
- Among 90 permanently implanted patients, there were three study-related infections, two wound dehiscences, one impaired-healing event, and two explants.
- Epidural leads and a subcutaneous pulse generator require surgery, and reversal requires another procedure.
Chamgap Semantic Classification Code
Candidate index · review held
P.10-khz-spinal-cord-stimulation.device.at-least-50-percent-pain-relief-in-refractory-painful-diabetic-neuropathy.relieve.MULTIProcedures, devices and tests > 10-kHz spinal cord stimulation > Device delivered > At least 50% pain relief in refractory painful diabetic neuropathy > Symptom-relief claim > Multiple: primary unresolved
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
Eighteen US sites randomized 216 participants. The allocation quote is "Treatment allocations were concealed with computer assignment 1:1" using "a random-sized block method by site and stratified by pain severity (VAS) and glycemic control." Defect name: Unblinded subjective endpoint. Listed item: Unblinded subjective endpoint. Original evidence that the requirement was met: the trial was described as "prospective, multicenter, open-label," and its primary composite included patient-reported VAS pain. Avoidability: Avoidable - paresthesia-free 10-kHz stimulation allowed device-off sham programming after identical implantation. Defect name: Active-only control. Listed item: Active-only control. Original evidence that the requirement was met: the comparison was "CMM or 10-kHz SCS plus CMM" without sham stimulation. Avoidability: Avoidable - a limited blinded device-off period was technically possible, although sham participants would face invasive procedural risk without active stimulation. The paper states, "This study was funded by Nevro Corp," and disclosed company employees and sponsor participation in design, analysis, interpretation, and writing.
Why this is classified as C (50)
The patient-centered response difference was large, but two avoidable design defects, no sham, and one Nevro-funded program limit the grade to C with 50 points.
Counterpoint. The large short-term signal matters, but independent sham-controlled replication and long-term explant, revision, and cost data are needed.
Rejudgment record. Direct source verification — Large patient-centered pain response, open-label subjective endpoint, active-only control, and one fully Nevro-funded trial
| Endpoint | P | Symptom or function itself is the target - including patient reports and performance tests |
| Replication | R1 | Single confirmatory trial |
| Independence | I0 | Evidence comes only from manufacturer studies |
| Effect size | E+ | Meets the clinically important threshold |
Stored derived and displayed grades match; this is not a current recalculation or validity check (C).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| At least 50% pain response at 3 months | C | The primary composite was 79% versus 5%, but the trial was open-label. |
| Long-term benefit outweighs procedural harm | ? | One 3-month randomized comparison cannot establish long-term revision, explant, and cost balance. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| Petersen EA et al. 2021 SENZA-PDN | Open-label 18-center randomized medical-management-controlled trial | 216 randomized (103/113); known 3-month status in 94/95 | Fully funded by Nevro Corp, with its device, employee coauthors, and sponsor roles in design, analysis, interpretation, and writing | At least 50% VAS pain relief at 3 months without meaningful worsening of baseline neurological deficits | 75/95 (79%) versus 5/94 (5%); absolute difference 73.6 points (95% CI 64.2 to 83.0) | Large patient-centered effect but open-label without sham and based on one manufacturer program |
Receipt — 2 References
All 2 cited sources were verified for existence at the original page (as of 2026-08-18).
Final verification and publication gate: Codex · Evidence date: 2026-08-18 · Corrections: none
Cite this verdict
[Chamgap] 10-kHz Spinal Cord Stimulation Benefits Refractory Painful Diabetic Neuropathy by Achieving at Least 50% Pain Relief — Evidence Grade C·50. 2 cited sources checked. Source: https://chamgap.com/en/verdicts/general/10khz-spinal-cord-stimulation-refractory-painful-diabetic-neuropathy/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.