
Catheter removal at 24 hours after TURP,
does it really help with Reduced catheter pain, discomfort, and hospital stay?
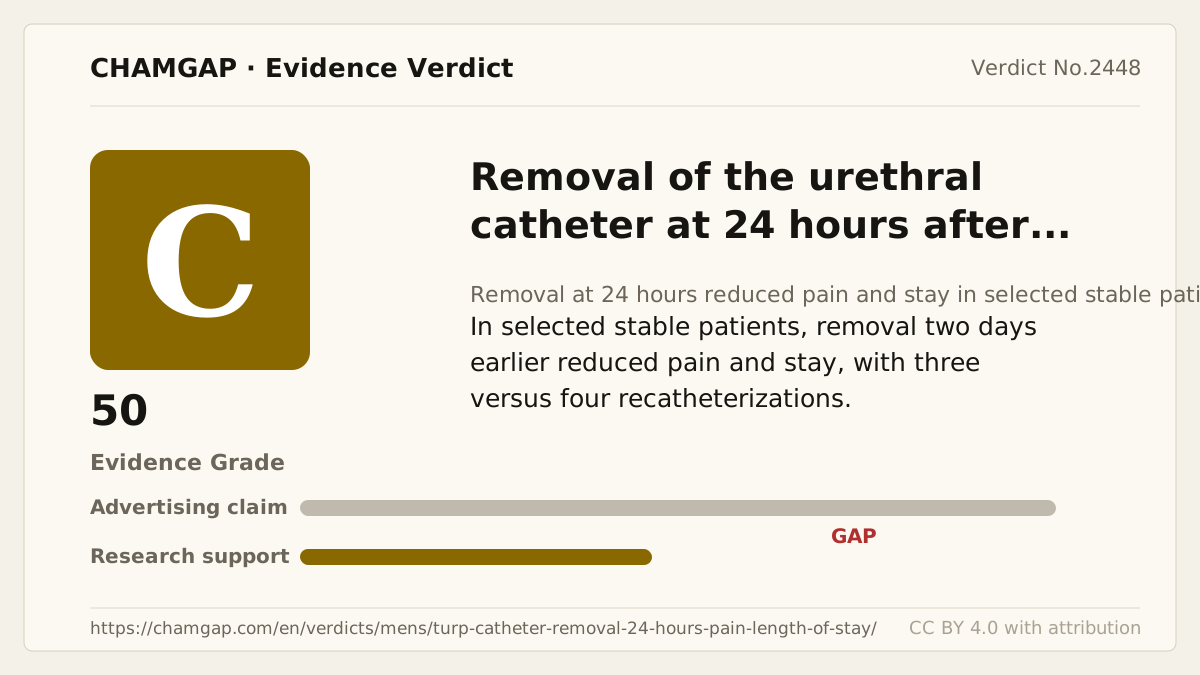
research showsThe grade is C with 50 points. In a 90-participant randomized trial, removal at 24 hours reduced stay and pain versus 72 hours. Recatheterization was 3/45 versus 4/45, and secondary bleeding was 6/45 versus 4/45. Group-specific absolute counts for acute urinary retention and severe hematuria were not reported. No prespecified primary endpoint and the NCT04363970 mismatch between a 48-hour registry control and a 72-hour paper control are two avoidable flaws.
ads claimKorean recovery pathways should not turn this into automatic removal and discharge at 24 hours. Irrigation must be stopped safely, drainage should be clear, and a voiding trial should succeed. Clots, inability to void, fever, or bright-red bleeding can require recatheterization or further observation.
Useful facts when choosing a product
- Registry NCT04363970 specified 24 versus 48 hours, while the paper reported 24 versus 72 hours; this was an avoidable flaw.
- Verdict 1433 is B with 72 points for long-term TURP itself; this verdict concerns post-TURP catheter timing.
- Recatheterization was 3/45 versus 4/45 and secondary bleeding was 6/45 versus 4/45, but group-specific counts for acute retention and severe hematuria were not reported.
Chamgap Semantic Classification Code
Candidate index · review held
P.removal-of-the-urethral-catheter-at-after-turp-in-eligible-stable-patients.procedural.catheter-pain-discomfort-and-hospital-stay.reduce.UNKProcedures, devices and tests > Removal of the urethral catheter at after TURP in eligible stable patients > Procedural > catheter pain, discomfort, and hospital stay > Reduction claim > Unknown
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
The Jordan University Hospital trial randomized 90 men after TURP, 45 to removal at 24 hours and 45 at 72 hours in the paper. Registry NCT04363970 instead specified a 48-hour delayed group, creating a protocol-publication mismatch. The paper also listed stay, pain, bladder discomfort, recatheterization, bleeding, and UTI without a prespecified single primary endpoint. These were the two avoidable flaws; the small 90-person sample was recorded separately. Stay was 2.83±0.43 versus 3.64±0.57 days and pre-removal pain 2.67±1.04 versus 3.73±1.18. Recatheterization was 3/45 versus 4/45 and secondary bleeding 6/45 versus 4/45. Acute retention and severe hematuria were stated reinsertion causes, but cause-specific counts for the seven events were not reported. Verdict 1433 is B with 72 points for the long-term effect of TURP itself versus observation; this verdict concerns when to remove the catheter after TURP. The corrected citation is FSO927, DOI 10.2144/fsoa-2023-0195.
Why this is classified as C (50)
No prespecified primary endpoint and the 48-versus-72-hour registry-paper mismatch give C with 50 points.
Counterpoint. Safety intervals are wide and high-risk surgical patients were excluded.
Rejudgment record. Cross-check applied — No prespecified primary endpoint and a 48-versus-72-hour registry-paper mismatch
| Endpoint | P | Symptom or function itself is the target - including patient reports and performance tests |
| Replication | R1 | Single confirmatory trial |
| Independence | I1 | Mixed funding sources |
| Effect size | E+ | Meets the clinically important threshold |
Stored derived and displayed grades match; this is not a current recalculation or validity check (C).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Reduced hospital stay | B | Mean stay was 0.81 days shorter with a large standardized difference. |
| Reduced catheter-related pain and bladder discomfort | B | Pain and discomfort were lower before and after removal. |
| No increase in recatheterization; acute-retention counts unreported by group | D | Recatheterization was 3/45 versus 4/45, but group-specific acute-retention and severe-hematuria counts and a precise noninferiority boundary were not reported. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| Al Demour S et al. 2024 | Randomized clinical trial of removal at 24 versus 72 hours | 90 randomized and analyzed (45/45) | Acknowledgments: The authors are thankful to Dr Sulaiman Al Habib Medical Group's Research Center for their tremendous support. No separate Funding section. | Stay, pain, bladder discomfort, recatheterization, bleeding, and UTI listed without a single primary endpoint | Stay 2.83±0.43 versus 3.64±0.57 days; pre-removal VAS 2.67±1.04 versus 3.73±1.18; recatheterization 3/45 versus 4/45; secondary bleeding 6/45 versus 4/45 | Pivotal single trial |
| Yu JJ et al. 2018 systematic review and meta-analysis | Synthesis of comparative early-versus-delayed removal studies | Total sample not verified in the accessible record | Funding wording not verified in the accessible record | Recatheterization and secondary hemorrhage | Recatheterization RR 1.12 (95% CI 0.73 to 1.72); secondary hemorrhage RR 1.07 (0.54 to 2.13) | Indirect pooled evidence on failure events |
Receipt — 2 References
All 2 cited sources were verified for existence at the original page (as of 2026-08-08).
Final verification and publication gate: Codex · Evidence date: 2026-08-08 · Corrections: none
Cite this verdict
[Chamgap] Catheter removal at 24 hours after TURP x reduced pain and hospital stay — Evidence Grade C·50. 2 cited sources checked. Source: https://chamgap.com/en/verdicts/mens/turp-catheter-removal-24-hours-pain-length-of-stay/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.