
Folic acid,
does it really help with Increase in source-defined category-a progressive motility in male-factor infertility?
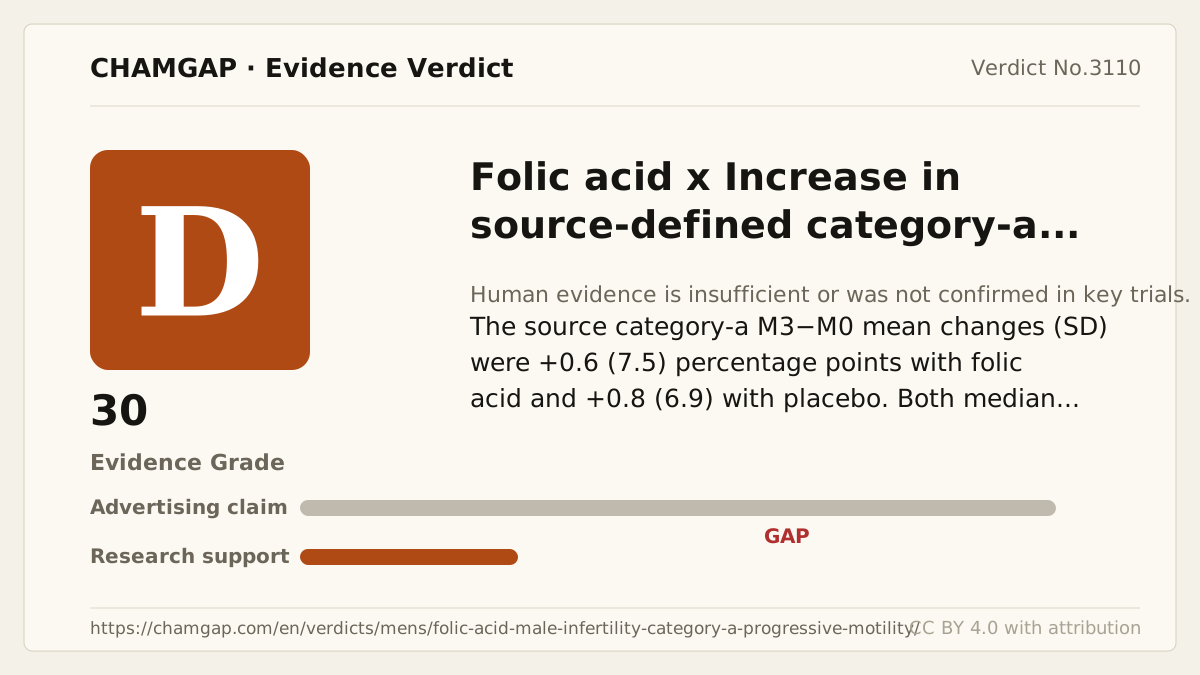
research showsThe direct placebo-controlled trial did not demonstrate improvement in the source category-a change at 3 months. D/30 is the current judgment for this narrow comparison, not proof of no effect for all folic-acid doses, aggregate WHO PR, pregnancy or live birth.
ads claimSperm motility, pregnancy, live birth and DNA outcomes are not interchangeable. Folic acid plus zinc is not folic acid alone.
Four separate assessment dimensions
| Effect direction and size | In FOLFIV, source-defined category-a motility change was +0.6 (SD 7.5) percentage points with folic acid and +0.8 (SD 6.9) with placebo; between-arm P=0.7871. Improvement was not demonstrated, but zero effect or equivalence was not established. |
|---|---|
| Evidence certainty | The axes are B / S / R1 / I2 / E0 / B1 / CX. Direct evidence is one trial at the exact boundary and public funding is a strength, while endpoint-specific attrition and an unverified between-arm CI and MCID remain. |
| Applicability | The claim is limited to folic acid 15 mg/day for 3 months in male partners aged 18–60 with at least one abnormal semen parameter and planned IVF-ICSI. Category a is not generalized to modern aggregate WHO PR, other doses, genotypes, semen measures, pregnancy or live birth. |
| Safety | Exact FOLFIV adverse-event counts and denominators remain unverified. Potential masking of B12 deficiency, antiepileptic/methotrexate interactions, long-term high-dose exposure and special-population limits are disclosed separately from efficacy. |
E0 means improvement was not demonstrated for the narrow comparison. One I2 strength gives the fixed D-band anchor of 30; F was not assigned because repeated refutation and exclusion of benefit were not established.
Useful facts when choosing a product
- The intervention was three folic-acid 5 mg tablets, totaling 15 mg/day, versus three daily placebo tablets matched in appearance, size, taste and weight. Bailly-Creat Laboratory manufacture was identified, but the exact salt, crystal form, release, batch, purity and placebo excipients remain unverified.
- The semen endpoint was at 3 months, while treatment could continue until IVF semen collection, so pregnancy follow-up is not equated with the semen visit. Adherence collection was planned, but actual ingestion rates and total dietary folate exposure remain unverified.
- The source separates Progressive motility (a) from Total motility (a+b+c). Category a is not automatically converted to modern aggregate WHO PR or historical a+b.
Chamgap Semantic Classification Code
Permanent code issued
M.folic-acid.oral-15mg-daily-3months.ivf-icsi-male-factor-infertility-category-a-progressive-motility.increase.matched-placeboMedicinal interventions > Folic acid monotherapy > Oral 15 mg/day for 3 months > Source-defined category-a progressive motility in male-factor infertility planning IVF-ICSI > Increase > Matched placebo
Fixed to the FOLFIV source-defined category-a change and kept separate from modern aggregate WHO PR, total motility, pregnancy and live birth. The code identifies the intervention and claim; it never contains the evidence grade, score, or safety result.
Exact Claim Classification
These independent facets prevent evidence from different forms, routes, populations, effects, and comparators from being mixed.
| Intervention class | M · Medicine |
|---|---|
| Canonical ingredient or intervention | Folic acid as the sole randomized additional active ingredient |
| Source or part used | Manufacturing source, salt and crystal form unverified; distinct from dietary folate, 5-MTHF and folinic acid |
| Formulation or processing | Three 5-mg tablets daily; matched placebo prepared by Bailly-Creat Laboratory; release, batch and excipients unverified |
| Route | Oral |
| Dose | 15 mg/day (three 5-mg tablets); timing and quantitative adherence unverified |
| Duration | Semen assessment at M3 (3 months); supplementation could continue until IVF semen collection, distinct from pregnancy follow-up |
| Population | Male partners aged 18–60 years in infertile couples planning IVF-ICSI; at least one abnormal semen criterion; mixed female causes present; not assumed to be confirmed folate-deficiency replacement |
| Effect or condition | Increase in the source-reported progressive-motility category a |
| Primary endpoint | Table4 Progressive motility (a), between-arm M3−M0 comparison, percentage points; published secondary endpoint; modern WHO aggregate PR crosswalk unverified |
| Comparator | Three matched placebo tablets daily on the same IVF-ICSI care policy; no other male hormonal or vitamin intervention reported |
| Duplicate-detection key | folic-acid|oral-tablet|15-mg-per-day|3-months|adult-male-factor-ivf-icsi|progressive-motility-as-reported-a|change-m3-m0|matched-placebo |
What the research actually shows
Table4 separately reports Progressive motility (a) and Total motility (a+b+c). The methods cite WHO 2010, but the exact speed threshold for category a and its correspondence to modern aggregate WHO PR were not verified. The page therefore retains the source category a, without converting it to a+b or total motility. This was an editorial boundary decision after the literature review, not a prospectively registered review plan.
Why this is classified as D (30)
The original 7 axes are B / S / R1 / I2 / E0 / B1 / CX. E0 means failure to demonstrate improvement in this exact comparison. I2 public funding provides 1 strength, giving the fixed D-band score of 30. Potential selection from missing outcomes is counted once under B1. Unverified CI/clinical importance is separated under precision, and other doses/genotypes under scope and replication. This is neither RX repeated refutation nor exclusion of benefit, so F was not assigned.
Counterpoint. In the same trial, biochemical pregnancy in the embryo-transfer subset occurred in 26/59 versus 11/49 couples, with Table6 P=0.018. Clinical pregnancy at 7 weeks occurred in 21/59 versus 10/49, P=0.082, a separate outcome. Miscarriage was 5/59 versus 1/49, P=0.146, with denominators explicitly not representing all randomized couples. These findings or DNA changes do not establish motility success or improved live birth.
| Endpoint | S | Surrogate marker - laboratory or imaging measures |
| Replication | R1 | Single confirmatory trial |
| Independence | I2 | Decisive evidence is publicly or non-profit funded |
| Effect size | E0 | Null |
| Precision | CX | No pooled confidence interval could be confirmed |
Review performed and remaining limitations
WHO category-a correspondence and speed threshold, full registry history, protocol, SAP, endpoint prespecification rank, missing-data sensitivity, between-arm CI and MCID, and product salt, batch, purity and excipients remain unverified.
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| FOLFIV primary trial | Double-blind parallel randomized matched-placebo trial | 162 randomized (83 versus 79); motility-change analysis 126 (66 versus 60) | French Ministry of Health PHRC 2010 public funding; AP-HP sponsorship | 3-month-minus-baseline change in source-defined category-a progressive motility (percentage points); article secondary endpoint | Mean change was +0.6 (SD 7.5) versus +0.8 (SD 6.9) percentage points; between-arm Wilcoxon–Mann–Whitney P=0.7871. Improvement was not demonstrated, but zero effect or equivalence was not established. | One decisive directly applicable trial family |
| da Silva 2013 | Randomized double-blind placebo-controlled folic-acid 5 mg/day monotherapy trial | 49 protocol completers; initial randomized count unverified | CAPES fellowships for two investigators; complete trial funding unverified | 3-month semen measures using a historical a+b motility definition | No significant improvement was reported for examined semen outcomes, but this is not the exact category-a estimand. | Adjacent evidence with a different dose and endpoint definition |
| Raigani 2014 | Four-arm randomized placebo-controlled trial including a folic-acid-only arm | 83 total; exact endpoint-specific denominator unverified | Unverified | Exact category-a effect estimate unverified in the abstract | Retained as a candidate but not counted toward direct replication or scoring. | Candidate with the exact endpoint unverified |
| Huang 2020 | MTHFR-genotype-stratified randomized placebo-controlled folic-acid 0.8 mg/day monotherapy trial | 769 eligible; overlapping genotype strata were not summed | Authors reported no funding | 3-month progressive motility in the MTHFR 677 TT subgroup | A positive TT-subgroup result was reported (32.36 to 40.63% versus 36.84 to 33.97%), but table-footnote and narrative test descriptions conflict, and the exact between-arm CI, P value and denominator remain unverified. | Positive adjacent evidence at a different dose and genotype |
| Wong 2002 | Factorial four-arm trial with a folic-acid-only arm and separate fertile/subfertile strata | Exact folic-only motility-analysis denominator unverified | PubMed reports non-US government support; details unverified | Exact category-a change estimate unverified | Retained as a monotherapy-arm candidate but not used as quantitative direct replication. | Candidate without recovered quantitative estimate |
| FAZST | Large randomized trial of combined folic acid 5 mg plus zinc 30 mg/day versus placebo | 2,370 participants | NIH/NICHD public support | Total motility and live birth; not folic-acid-only category-a motility | Total-motility difference was −0.5 percentage points (95.1% CI −2.5 to 1.5). The combination and different endpoint were not used as a folic-acid-only effect or repeated refutation. | Combination and different-endpoint exclusion evidence |
Receipt — 14 References
Evidence access cutoff: 2026-09-16. Each citation states its actual access level (full-text transcription, abstract, index, or other) and remaining limitations. Bibliographic checking does not certify the study results or treatment efficacy.
Technical integration by: Codex · Evidence date: 2026-09-16 · Corrections: none
Cite this verdict
[Chamgap] Does folic acid 15 mg/day improve category-a progressive motility in male infertility? — Evidence Grade D·30. 14 cited sources checked. Source: https://chamgap.com/en/verdicts/mens/folic-acid-male-infertility-category-a-progressive-motility/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.