
A five-day course of prednisone 40 mg,
does it really help with Noninferior six-month re-exacerbation after hospitalized acute COPD exacerbation versus 14 days?
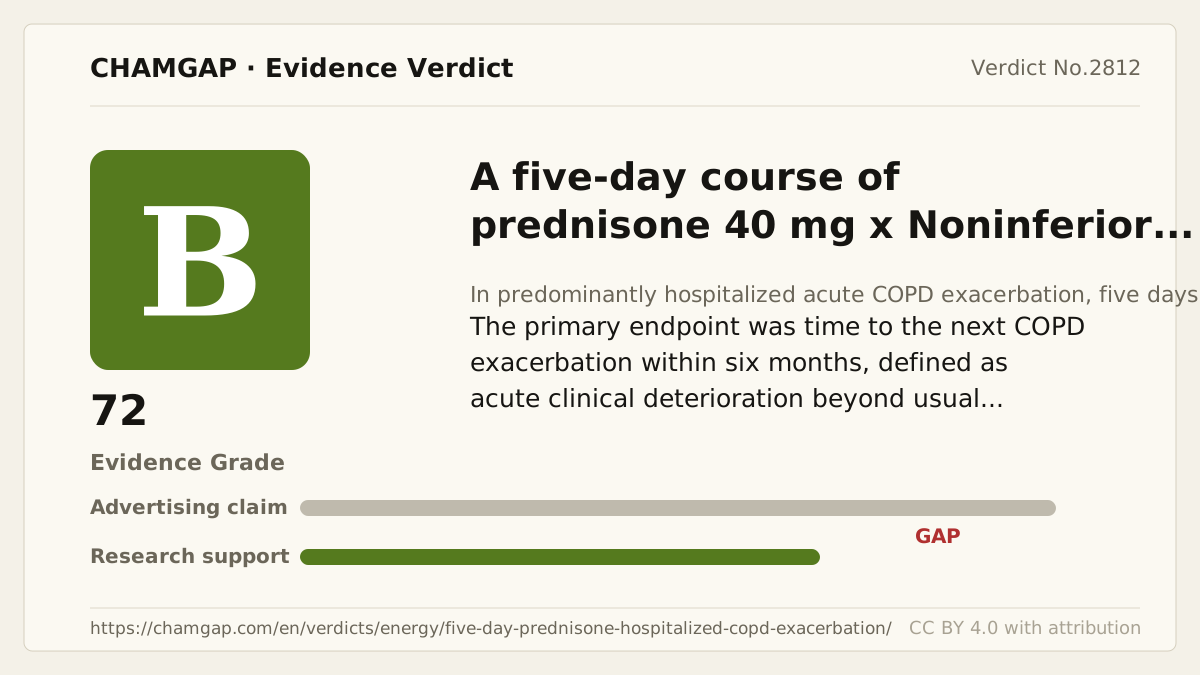
research showsThe grade is B. REDUCE randomized 314 patients and showed in both intention-to-treat and per-protocol analyses that five days did not worsen six-month re-exacerbation beyond the prespecified margin. Events occurred in 35.9% versus 36.8%; estimated 180-day rates were 37.2% versus 38.4%, an absolute difference of -1.2 points (95% CI -12.2 to 9.8).
ads claimThis verdict asks how many days to use steroids after an exacerbation has already occurred. Verdict 1195 is B with 75 points for azithromycin prevention in exacerbation-prone COPD; verdict 2562 is C with 56 points for oxygen targets during transport; verdict 1727 is D with 25 points for cough in nonasthmatic lower respiratory infection, not COPD.
Useful facts when choosing a product
- Mean cumulative prednisone exposure was 379 mg with five days versus 793 mg with 14 days.
- Treatment-associated hyperglycemia and hypertension were not significantly more frequent with the longer course.
- The evidence applies to the tested 40 mg/day regimen and predominantly admitted population.
Chamgap Semantic Classification Code
Candidate index · review held
UNK.course-of-prednisone.UNK.re-exacerbation-after-hospitalized-acute-copd-exacerbation.noninferior.usual-careUnknown > course of prednisone > Unknown > re-exacerbation after hospitalized acute COPD exacerbation > Noninferiority claim > Usual care
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
A centralized secure website concealed allocation, and patients, caregivers, outcome assessors, data collectors, the biostatistician, and investigators remained blinded through the primary analysis. Of 314 randomized, 311 were in ITT and 296 per protocol; participants lost later were censored at last contact and retained. The sole named avoidable limitation is noninferiority design. A no-steroid arm was not counted because it would withdraw standard acute-exacerbation treatment. Investigator-initiated support mixed Swiss hospitals and foundations with AstraZeneca and Viollier Laboratory. Sponsors had no role in design, conduct, data, analysis, manuscript, or publication decisions, while authors disclosed multiple industry relationships.
Why this is classified as B (72)
A single 314-patient hard-event trial met prespecified 15-point and HR 1.515 margins in both ITT and per-protocol analyses; noninferiority design and mixed funding give B with 72 points.
Counterpoint. This establishes noninferiority with less exposure, not superior prevention of re-exacerbation.
Rejudgment record. Source and registry cross-check — Six-month clinical re-exacerbation, prespecified 15-point and HR 1.515 margins, consistent ITT and per-protocol findings, noninferiority design and mixed funding
| Endpoint | H | Hard endpoint - actual events such as death |
| Replication | R1 | Single confirmatory trial |
| Independence | I1 | Mixed funding sources |
| Effect size | E+ | Meets the clinically important threshold |
Stored derived and displayed grades match; this is not a current recalculation or validity check (B).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Noninferior six-month re-exacerbation | B | Both ITT and per-protocol analyses stayed within the prespecified HR 1.515 margin. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| Leuppi JD et al. 2013 REDUCE | Multicenter double-blind randomized noninferiority trial | 314 randomized; 311 in ITT; 296 per protocol | Mixed support from Swiss hospitals and academic foundations plus AstraZeneca and Viollier Laboratory; sponsors had no stated role | Time to the next COPD exacerbation within six months | Events 35.9% versus 36.8%; HR 0.95 (90% CI 0.70 to 1.29) ITT and 0.93 (0.68 to 1.26) per protocol; estimated absolute difference -1.2 points (95% CI -12.2 to 9.8) | Large clinical-event noninferiority evidence |
Receipt — 1 References
All 1 cited sources were verified for existence at the original page (as of 2026-08-18).
Final verification and publication gate: Codex · Evidence date: 2026-08-18 · Corrections: none
Cite this verdict
[Chamgap] Short-Term vs Conventional Glucocorticoid Therapy in Acute Exacerbations of COPD - Benefit — Evidence Grade B·72. 1 cited sources checked. Source: https://chamgap.com/en/verdicts/energy/five-day-prednisone-hospitalized-copd-exacerbation/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.