
Low-dose aspirin,
does it really help with Primary prevention of myocardial infarction and stroke in healthy older adults without cardiovascular disease?
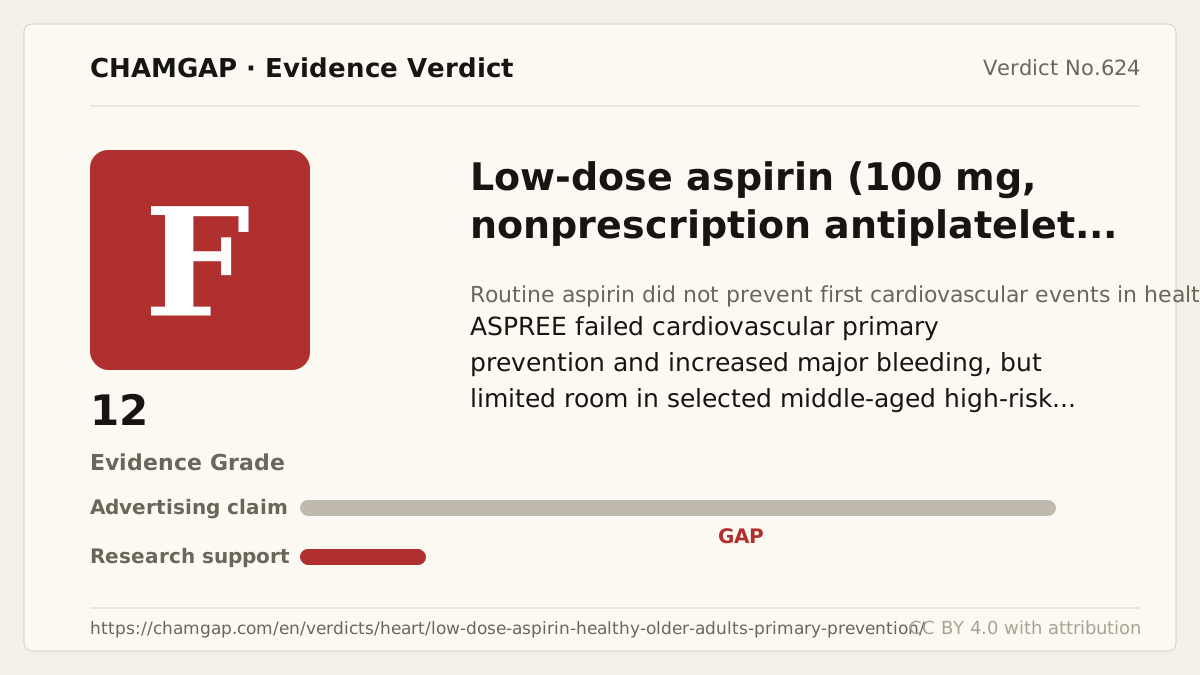
research showsThe claim that low-dose aspirin 100 mg prevents a first myocardial infarction or stroke in healthy older adults without cardiovascular disease is rated F. The independent double-blind ASPREE trial followed 19,114 participants for a median of 4.7 years, found no significant cardiovascular benefit (HR 0.95), and increased major hemorrhage (HR 1.38). The USPSTF also recommends against initiating aspirin for primary prevention at age 60 or older. The score is F with 12 points because primary prevention has not been repeatedly refuted across every age and risk stratum, and a small net benefit may remain possible in selected high-risk adults aged 40 to 59. Established secondary prevention is a separate pathway, not contradictory evidence.
ads claimThe idea that aspirin thins blood and cleans vessels presents platelet inhibition as pure benefit. Gastrointestinal and intracranial bleeding can increase even when thrombotic events do not fall, and nonprescription status does not prove efficacy or safety for daily preventive use.
Useful facts when choosing a product
- Low-dose aspirin 100 mg irreversibly inhibits platelet COX-1. Although available without a prescription, daily primary-prevention use requires assessment of age, cardiovascular risk, bleeding risk, and interacting medicines.
- ASPREE studied healthy older adults without established cardiovascular disease, a population distinct from secondary prevention after myocardial infarction or ischemic stroke. Anyone taking clinician-directed aspirin should not stop solely because of this verdict.
- This antiplatelet primary-prevention pathway also differs from lipid and cardiovascular claims involving omega-3 products or red yeast rice. Results cannot be substituted across ingredients or populations.
- Gastrointestinal bleeding, peptic ulcer, intracranial hemorrhage, and anemia can occur, while anticoagulants, other antiplatelets, nonsteroidal anti-inflammatory drugs, and alcohol can increase risk. Black stools, vomiting blood, sudden severe headache, or neurologic deficits require urgent assessment.
Chamgap Semantic Classification Code
Candidate index · review held
M.aspirin.UNK.primary-prevention-of-myocardial-infarction-and-stroke-without-cardiovascular-disease.prevent.placeboMedicinal interventions > aspirin > Unknown > Primary prevention of myocardial infarction and stroke without cardiovascular disease > Occurrence-prevention claim > Placebo
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
ASPREE randomized 19,114 older adults without known cardiovascular disease, dementia, or major disability to aspirin 100 mg daily or placebo. Participants were generally at least 70 years old in Australia or at least 65 among selected United States minority groups. At a median 4.7 years, the cardiovascular composite was null at HR 0.95 and major hemorrhage increased at HR 1.38. The concurrently published mortality analysis reported HR 1.14 for all-cause death, driven by cancer mortality but inconsistent with earlier evidence and therefore requiring caution. This was not a trial of secondary prevention after myocardial infarction or stroke.
Why this is classified as F (12)
The independent double-blind 19,114-participant ASPREE trial did not significantly reduce direct cardiovascular outcomes including myocardial infarction and stroke (HR 0.95) and significantly increased major hemorrhage (HR 1.38). The USPSTF recommends against initiation at age 60 or older, confirming F for healthy older-adult primary prevention. Because evidence does not repeatedly refute every age and risk stratum and selected high-risk adults aged 40 to 59 may retain a small net benefit, the score is 12 rather than the bottom of F. Established secondary prevention is a separate pathway, not contradictory evidence.
Counterpoint. Primary prevention in some younger adults at high cardiovascular risk is a different individualized net-benefit question. This F verdict is limited to routine initiation in healthy older adults without cardiovascular disease.
Rejudgment record. New verdict — Confirmed F because ASPREE found no cardiovascular benefit in 19,114 healthy older adults (HR 0.95) and increased major hemorrhage (HR 1.38), while reflecting limited potential net benefit in selected high-risk adults aged 40 to 59 and the separate established secondary-prevention pathway in the score
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Primary prevention of myocardial infarction and stroke in healthy older adults | F | An independent 19,114-participant trial did not significantly reduce direct cardiovascular outcomes. |
| Secondary prevention after established myocardial infarction or stroke | A | This is an established separate indication pathway; the F verdict for healthy older-adult primary prevention does not apply. |
| Major gastrointestinal or intracranial bleeding | A | ASPREE directly demonstrated a significant increase in major hemorrhage as a safety outcome. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| McNeil JJ et al., ASPREE cardiovascular and bleeding analysis 2018 | Multinational randomized double-blind placebo-controlled trial | 19,114 healthy older adults followed for a median of 4.7 years | Public funding including the United States NIA and NCI and Australian NHMRC; Bayer supplied study drug but did not direct design or conduct | Fatal coronary disease, nonfatal myocardial infarction, stroke, heart-failure hospitalization, and major hemorrhage | No cardiovascular benefit at HR 0.95; major hemorrhage increased at HR 1.38 | Independent large direct null-efficacy and harm evidence |
| McNeil JJ et al., ASPREE all-cause mortality analysis 2018 | Prespecified mortality analysis of the same randomized trial | 19,114 participants and 1,052 deaths | Public funding including NIA, NCI, and NHMRC | All-cause and cause-specific mortality | All-cause mortality HR 1.14, unexpectedly driven by cancer death and requiring cautious interpretation | Supports absent net benefit with an exploratory harm signal |
Receipt — 3 References
All 3 cited sources were verified for existence at the original page (as of 2026-07-19).
Final verification and publication gate: Codex · Evidence date: 2026-07-19 · Corrections: none
Cite this verdict
[Chamgap] Low-dose aspirin x cardiovascular primary prevention in healthy older adults — Evidence Grade F·12. 3 cited sources checked. Source: https://chamgap.com/en/verdicts/heart/low-dose-aspirin-healthy-older-adults-primary-prevention/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.