
Dexamethasone,
does it really help with Reduced 28-day mortality in hospitalized COVID-19?
research showsThe grade is B. In the open-label RECOVERY trial, the primary 28-day mortality outcome was 482/2,104 (22.9%) with dexamethasone versus 1,110/4,321 (25.7%) with usual care, rate ratio 0.83 (95% CI 0.75 to 0.93). Benefit was confined to patients requiring respiratory support.
ads claimVerdict 1372 is B with 68 points for an intravitreal implant, verdict 1511 is B with 68 points for adult bacterial meningitis, verdict 1693 is A with 82 points for pediatric croup, and verdict 1698 is D with 34 points for acute sore throat. These are different indications and routes.
Useful facts when choosing a product
- Dexamethasone is a systemic prescription glucocorticoid.
- RECOVERY used 6 mg daily for up to 10 days or discharge.
- The control was usual care rather than placebo.
- Results differed by baseline respiratory support.
Chamgap Semantic Classification Code
Candidate index · review held
M.dexamethasone-orally-or-intravenously-once.MULTI.mortality-in-hospitalized-covid-19.reduce.usual-careMedicinal interventions > Dexamethasone orally or intravenously once > Multiple: primary unresolved > mortality in hospitalized COVID-19 > Reduction claim > Usual care
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
This was an open-label randomized platform trial in 176 UK hospitals comparing 6 mg daily for up to 10 days with usual care. Mortality was objective and follow-up was nearly complete. Other independent randomized trials generally tested another corticosteroid, another dose, or a different primary endpoint; no independent direct replication of the same 6 mg dexamethasone comparison and 28-day mortality population was confirmed.
Why this is classified as B (76)
A large publicly funded randomized trial reduced an objective mortality endpoint, and open-label assignment did not create a major avoidable defect for death ascertainment. Lack of direct independent replication gives B with 76 points.
Counterpoint. Class-wide steroid meta-analysis was supportive but was not counted as direct replication of this exact dexamethasone question.
Rejudgment record. Cross-check applied — Respiratory-support subgroup event counts, the 28-day primary outcome, open-label design, and lack of direct replication were checked
| Endpoint | H | Hard endpoint - actual events such as death |
| Replication | R1 | Single confirmatory trial |
| Independence | I2 | Decisive evidence is publicly or non-profit funded |
| Effect size | E+ | Meets the clinically important threshold |
Stored derived and displayed grades match; this is not a current recalculation or validity check (B).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Reduced 28-day mortality with invasive ventilation | B | Mortality was 29.3% versus 41.4%. |
| Reduced 28-day mortality with oxygen alone | B | Mortality was 23.3% versus 26.2%. |
| Reduced mortality without oxygen | D | Rates were 17.8% versus 14.0%, with no benefit and possible harm. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| RECOVERY Collaborative Group 2021 | Multicenter randomized open-label platform trial | 6,425 randomized and analyzed by intention to treat | Medical Research Council, National Institute for Health Research, and other public or nonprofit support | Primary outcome: 28-day all-cause mortality | 482/2,104 (22.9%) vs 1,110/4,321 (25.7%); rate ratio 0.83 (95% CI 0.75 to 0.93) | Decisive direct evidence |
Receipt — 1 References
All 1 cited sources were verified for existence at the original page (as of 2026-08-07).
Final verification and publication gate: Codex · Evidence date: 2026-08-07 · Corrections: none
Cite this verdict
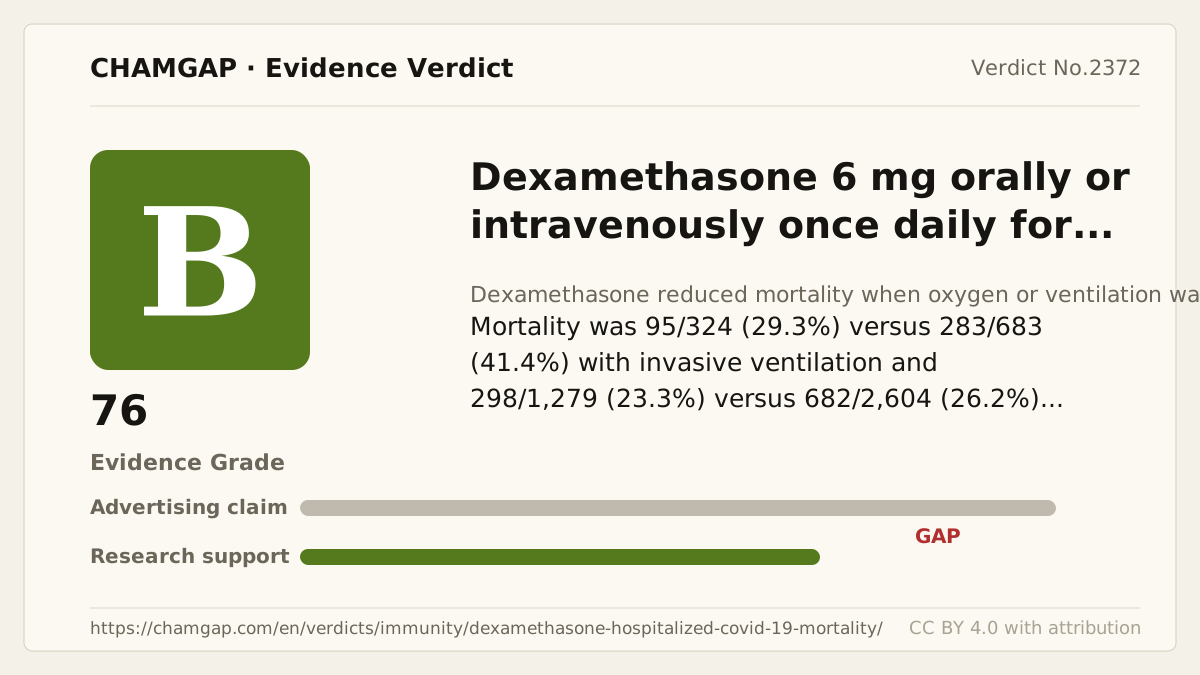
[Chamgap] Dexamethasone x reduced mortality in hospitalized COVID-19 — Evidence Grade B·76. 1 cited sources checked. Source: https://chamgap.com/en/verdicts/immunity/dexamethasone-hospitalized-covid-19-mortality/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.