
Beta-lactam monotherapy strategy,
does it really help with Noninferior 90-day mortality versus combination antibiotic strategies in adults hospitalized outside the ICU with community-acquired pneumonia?
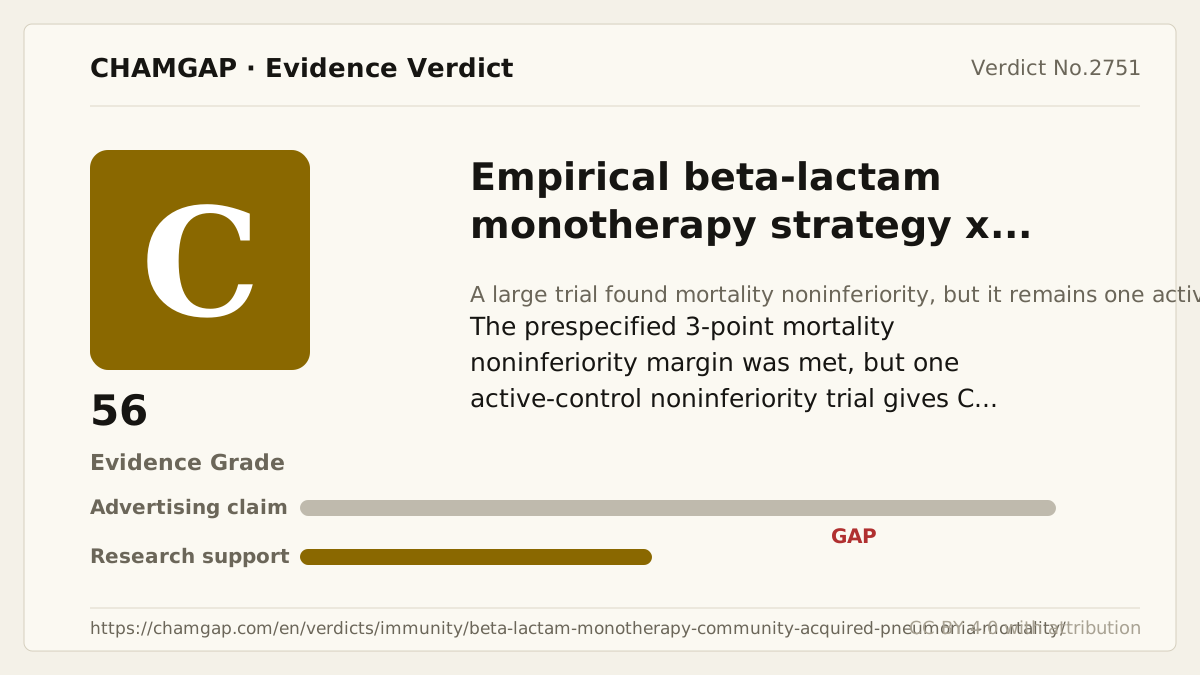
research showsThe grade is C. CAP-START analyzed all 2,283 patients included during the strategy periods across seven hospitals. Ninety-day mortality was 9.0% with beta-lactam monotherapy, 11.1% with beta-lactam plus macrolide, and 8.8% with fluoroquinolone. Monotherapy met the prespecified 3-point noninferiority margin, but evidence remains one noninferiority trial with active comparators, giving C with 56 points.
ads claimNoninferiority means the mortality result stayed within the prespecified 3-point margin; it does not mean monotherapy reduced mortality more. Choice still depends on severity, allergy, resistance, pathogens, and local guidance.
Useful facts when choosing a product
- Ninety-day mortality across the three strategies was 9.0%, 11.1%, and 8.8%.
- The intervention was a preferred hospital empirical strategy rather than one fixed drug.
- Public funding was stated; no company provision of study drugs or devices was identified.
Chamgap Semantic Classification Code
Candidate index · review held
M.empirical-beta-lactam-monotherapy-strategy.UNK.mortality.noninferior.activeMedicinal interventions > Empirical beta-lactam monotherapy strategy > Unknown > mortality > Noninferiority claim > Active comparator
An automated migration candidate, not an issued permanent code; exact claim scope remains under review. This machine-generated migration candidate helps retrieval but is not a permanent assignment. The original verdict ID and URL remain authoritative.
What the research actually shows
CAP-START rotated three four-month strategies across seven Dutch hospitals and randomized each hospital's sequence using computer-generated blocks. Strategy assignment was open, but 90-day mortality was obtained from hospital or municipal population records. Intention-to-treat analysis included all 2,283 patients according to the strategy period. Adjusted absolute differences versus beta-lactam were +1.9 points (90% CI -0.6 to 4.4) for beta-lactam plus macrolide and -0.6 points (-2.8 to 1.9) for fluoroquinolone. The article names the Netherlands Organization for Health Research and Development as funder.
Why this is classified as C (56)
A large publicly funded mortality trial met its prespecified noninferiority criterion, but the single active-control noninferiority design limits the verdict to C with 56 points.
Counterpoint. Mortality noninferiority does not establish superiority for resistance, adverse effects, or pathogen-specific outcomes.
Rejudgment record. Cross-check applied — Balances prespecified mortality noninferiority in a 2,283-patient publicly funded trial against the single active-control noninferiority design
| Endpoint | H | Hard endpoint - actual events such as death |
| Replication | R1 | Single confirmatory trial |
| Independence | I2 | Decisive evidence is publicly or non-profit funded |
| Effect size | E+ | Meets the clinically important threshold |
Stored derived and displayed grades match; this is not a current recalculation or validity check (C).
Sub-claim grades by effect
This ingredient is marketed for several effects. A single overall grade blends strong and weak claims together, so each effect is graded separately here. The overall grade reflects the strongest disconfirming or core claim.
| Effect (sub-claim) | Grade | Basis |
|---|---|---|
| Noninferior 90-day mortality | C | The prespecified 3-point margin was met, but evidence is one active-control noninferiority trial. |
| Mortality superiority over combination strategies | D | The trial did not establish superiority. |
Cross-check — AI research and Codex final gate
Evidence Table
| Study | Design | Sample | Funding | Endpoint | Result | Weight |
|---|---|---|---|---|---|---|
| Postma DF et al. 2015 CAP-START | Seven-hospital cluster-randomized three-period crossover noninferiority trial | 2,283 included and analyzed by intention to treat, 656/739/888 | Netherlands Organization for Health Research and Development | All-cause mortality at 90 days | 9.0% versus 11.1% versus 8.8%; adjusted differences versus beta-lactam +1.9 points (90% CI -0.6 to 4.4) and -0.6 points (-2.8 to 1.9), meeting the 3-point margin | Single large publicly funded mortality trial with noninferiority and active-control limitations |
Receipt — 1 References
All 1 cited sources were verified for existence at the original page (as of 2026-08-18).
Final verification and publication gate: Codex · Evidence date: 2026-08-18 · Corrections: none
Cite this verdict
[Chamgap] Beta-lactam monotherapy strategy x 90-day mortality in hospitalized community-acquired pneumonia — Evidence Grade C·56. 1 cited sources checked. Source: https://chamgap.com/en/verdicts/immunity/beta-lactam-monotherapy-community-acquired-pneumonia-mortality/ · CC BY 4.0CC BY 4.0 — free to use with attribution; do not distort grades, numbers, or verdict meaning.
What this document does and does not do
Chamgap is an information source. It reports what research has and has not confirmed; it does not tell readers what to take or buy. That decision belongs to readers and, when needed, medical or legal professionals. This verdict reflects literature available up to the search date and may change as new research appears. Nothing here is medical advice.